TAVR: Procedure, Benefits, Risks and Recovery
Transcatheter Aortic Valve Replacement (TAVR, also termed TAVI) is a landmark minimally invasive structural heart procedure that replaces a calcified, narrowed aortic valve without open-heart surgery. Specifically, a bioprosthetic valve mounted on an expandable stent frame is threaded through the femoral artery to immediately restore unobstructed blood flow from the left ventricle. In addition, this evidence-based clinical guide details TAVR procedural steps, CT sizing protocols, TAVR vs SAVR comparisons, and specialist recovery guidance reviewed by certified structural heart cardiologists.
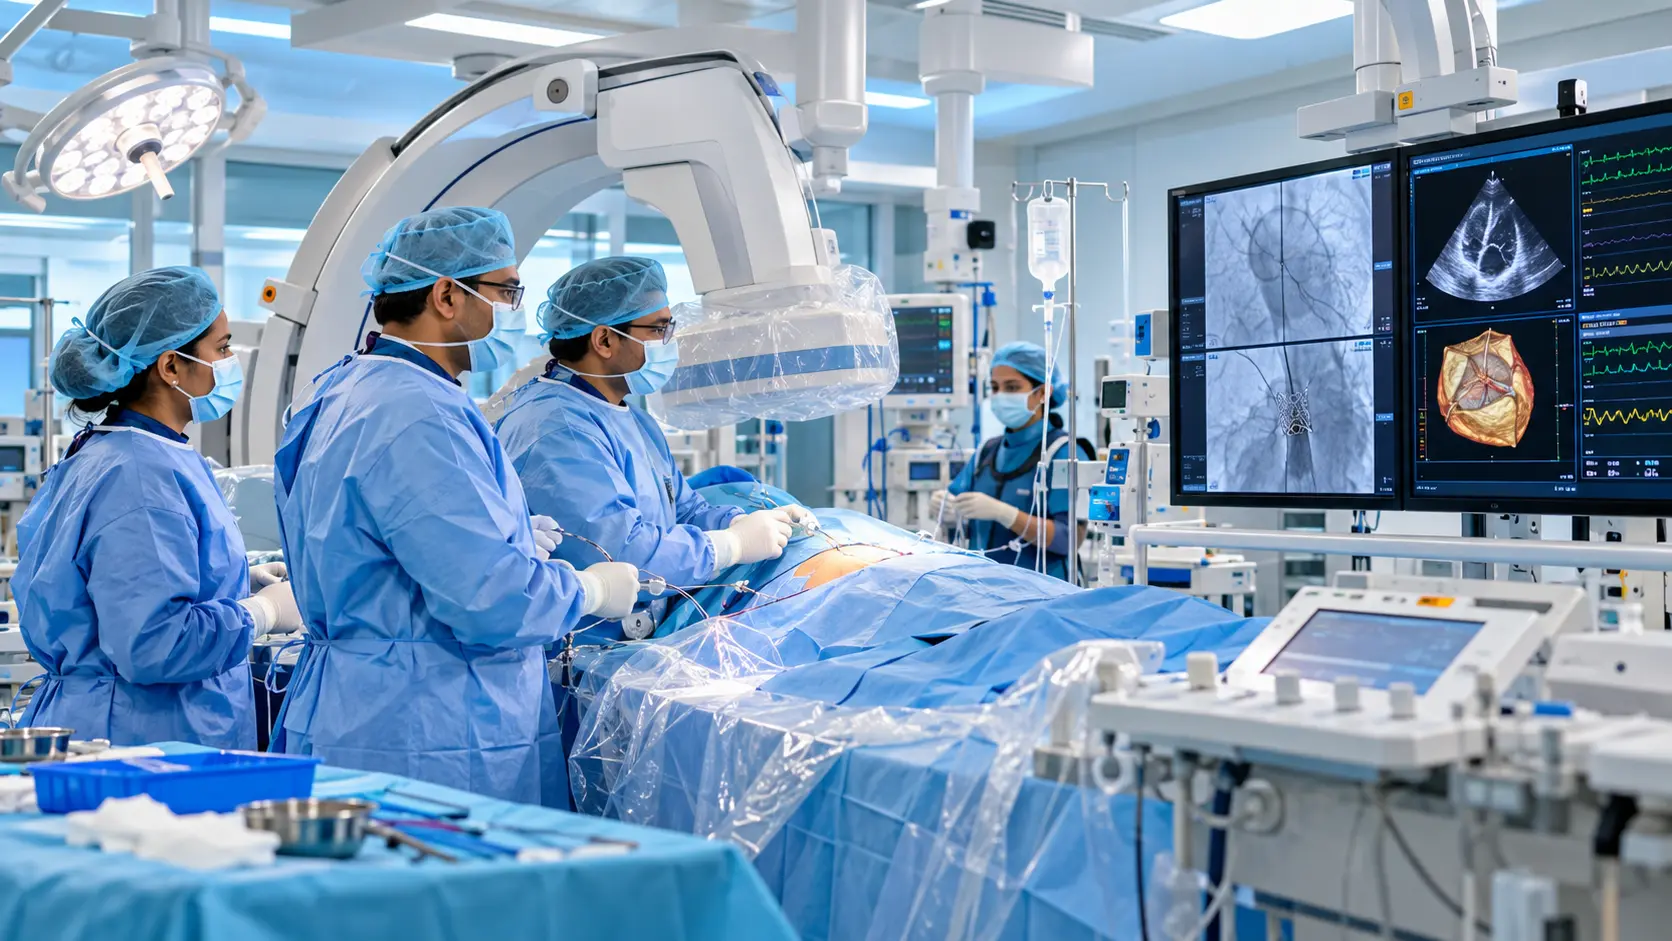

Dr. Siddharth Sonkamble
Senior Interventional Cardiologist & TAVR Specialist
MBBS, MD, DM (Cardiology), FESC, FSCAI
Understanding TAVR: Transcatheter Aortic Valve Replacement Essentials
Specifically, severe aortic stenosis is a progressive, life-limiting condition in which calcium accumulation hardens the aortic valve leaflets, obstructing blood flow from the left ventricle into the systemic circulation. Historically, open-heart surgical aortic valve replacement (SAVR) with sternotomy was the sole therapeutic option. Today, TAVR offers a proven, minimally invasive catheter-based alternative that restores normal valve hemodynamics without chest opening or cardiopulmonary bypass.

TAVR immediately relieves breathlessness, chest heaviness, and syncopal episodes by expanding the narrowed aortic valve area.
Additionally, performed through a 6 mm groin puncture under conscious sedation, allowing patients to walk within hours.
🩺 TAVR Patient Quick Facts
- ✓ Therefore, procedure Duration: Approximately 45 to 90 minutes.
- ✓ Overall, anesthesia: Conscious sedation in >80% of patients.
- ✓ In addition, hospital Stay: Typically 24 to 48 hours.
- ✓ Moreover, valve Longevity: Robust durability demonstrated past 10 years.
What Is TAVR (Transcatheter Aortic Valve Replacement)?
As a result, understanding the mechanism of catheter-based aortic valve replacement.
TAVR (Transcatheter Aortic Valve Replacement), also referred to internationally as TAVI (Transcatheter Aortic Valve Implantation), is an advanced cardiac intervention designed to replace a diseased, stenotic aortic valve through the inside of blood vessels rather than by cutting open the chest.
Specifically, the aortic valve acts as the main gateway from the left ventricle into the aorta, controlling the outflow of oxygen-rich blood to the entire body. When calcific aortic stenosis develops, the valve leaflets become stiff, thickened, and fused, preventing the valve from opening fully. Consequently, the heart muscle must pump against extreme resistance, leading to cardiac hypertrophy, heart failure, and life-threatening arrhythmias.
In addition, during a TAVR procedure, a collapsible artificial bioprosthetic valve (crafted from natural bovine or porcine pericardial tissue mounted onto an expandable cobalt-chromium or nitinol metal stent frame) is crimped onto a thin delivery catheter. Subsequently, the interventional team guides the catheter through the femoral artery in the leg directly into the heart. Accordingly, once positioned precisely within the calcified native valve, the new valve is expanded, pushing the diseased native leaflets aside and immediately taking over the function of regulating cardiac blood flow.
Core Aortic Valve Anatomical Principles
Unlike surgical replacement where the old calcified valve is physically excised, TAVR uses the existing calcified leaflets to firmly anchor the new prosthetic stent frame inside the aortic annulus, eliminating the need for surgical sutures or cardiac arrest.
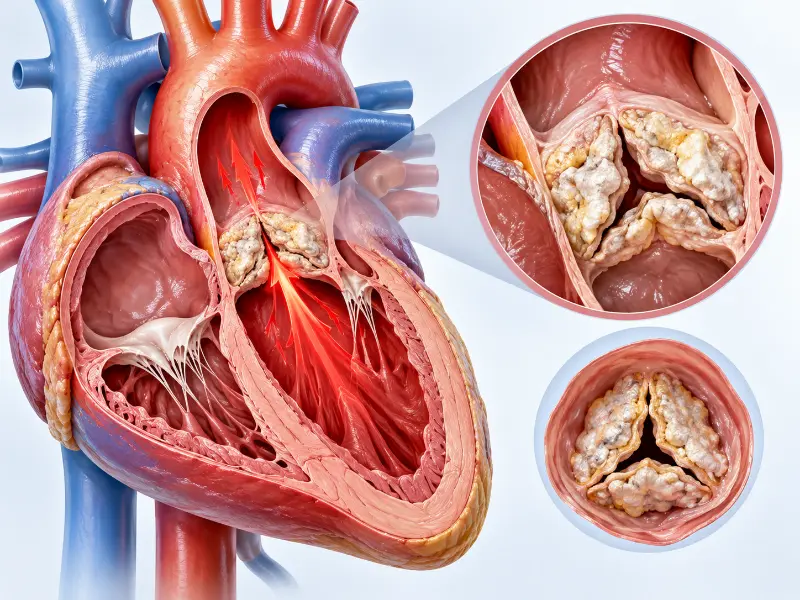
Transcatheter Therapy for Pure Native Aortic Regurgitation & Clipping Devices
For example, historically, standard TAVR devices received regulatory approval exclusively for calcific aortic stenosis, where heavy calcium deposits firmly anchor the expanding stent. In contrast, pure native aortic regurgitation (AR)—valve incompetence leading to severe backward leakage without calcification—presented an anatomical challenge because conventional self-expanding or balloon-expandable valves had no calcific ledge to grasp.
Specifically evaluated dedicated transcatheter devices (such as the JenaValve Trilogy Heart Valve System) in high-risk patients with symptomatic, severe pure native AR. Hence, demonstrates robust primary efficacy and safety endpoints, eliminating open-heart valve surgery.
Thus, features proprietary anatomical locators that physically clip onto the native valve leaflets. At the same time, this novel mechanism guarantees rock-solid coaxial fixation, prevents device migration, and delivers total paravalvular seal even in totally non-calcified aortic roots.
Why Is TAVR Recommended for Severe Aortic Stenosis?
Undoubtedly, evidence-based guidelines, surgical risk categories, and clinical presentation.
Overall, medical therapy alone (such as diuretics or blood pressure tablets) cannot mechanically relieve the physical obstruction of a calcified, narrowed aortic valve. Above all, once a patient with severe aortic stenosis develops hallmark symptoms—known medically as the classic triad of angina (chest pain), syncope (dizziness/fainting), and heart failure (exertional breathlessness)—the survival prognosis without valve replacement drops dramatically to approximately 50% at two years. Therefore, timely intervention with TAVR is lifesaving.
Primary TAVR Clinical Indications & Aortic Stenosis Criteria
Specifically, TAVR is recommended for patients diagnosed with severe symptomatic high-gradient aortic stenosis (mean gradient ≥40 mmHg, peak jet velocity ≥4.0 m/s, or valve area ≤1.0 cm²), as well as low-flow low-gradient aortic stenosis confirmed by dobutamine stress echocardiography.
Heart Team Evaluation & Surgical Risk Stratification Protocol
Furthermore, global ACC/AHA and ESC guidelines approve TAVR across high-risk, intermediate-risk, and low-risk surgical categories. A Besides, multidisciplinary Heart Team evaluates the patient’s STS score, EuroSCORE II, frailty, porcelain aorta, and transfemoral access anatomy.
Hemodynamic Shock & Urgent TAVR Clinical Protocols
In addition, in patients presenting with acute decompensated heart failure or cardiogenic shock caused by severe critical aortic stenosis, urgent or emergency TAVR can rapidly unload the left ventricle, restore systemic perfusion, and avert cardiovascular collapse.

Asymptomatic Severe Aortic Stenosis & The Early Intervention Paradigm
Historically, clinical guidelines advocated “watchful waiting” until patients reported classic symptoms of chest pain, dizziness, or breathlessness. However, the landmark EARLY TAVR Randomized Trial presented at TCT and published in the New England Journal of Medicine (2024) demonstrated a decisive paradigm shift.
Early intervention with TAVR reduced the composite rate of all-cause mortality, stroke, or unplanned cardiovascular hospitalization by approximately 50% compared to clinical surveillance. Certainly, in the watchful waiting arm, over 25% of patients rapidly decompensated within 6 months, confirming that waiting for symptoms risks irreversible left ventricular myocardial fibrosis.
Sex-Specific Considerations in Valve Replacement: Anatomical Nuances in Women
First, women account for nearly half of all TAVR candidates globally but present with distinct anatomical geometry and pathophysiology that require dedicated procedural customization:
- On the whole, smaller Annulus & Lower Coronary Heights: Women typically have smaller aortic annuli and lower coronary ostia, necessitating precise virtual CT modeling to prevent coronary impingement.
- Further, paradoxical Low-Flow Prevalence: Concentric left ventricular remodeling is more frequent in females, requiring sex-specific CT calcium thresholds (>1,200 Agatston units for females vs. >2,000 for males).
- Greater Long-Term Survival Gain: Registry data confirms that women achieve superior long-term survival with TAVR compared to open surgery (SAVR), primarily due to avoiding prosthesis-patient mismatch in smaller roots.
Occult Cardiac Amyloidosis & Aortic Stenosis: Dual Pathology Screening Protocol
To clarify, first, up to 16% of Old Aged severe aortic stenosis patients carry undiagnosed Transthyretin Cardiac Amyloidosis (ATTR-CM). Likewise, our clinical pathway integrates 99mTc-PYP scintigraphy bone scans and 2D speckle-tracking echocardiography (apical sparing strain pattern) to screen all high-suspicion candidates.
Relieving the mechanical valve afterload via TAVR significantly improves cardiac hemodynamics, enabling safe long-term initiation of targeted transthyretin tetramer stabilizers (Tafamidis) to halt amyloid fibril infiltration and prolong life expectancy.
Moderate Aortic Stenosis with Heart Failure: The TAVR UNLOAD & PROGRESS Clinical Frontier
In addition, emerging multicenter randomized clinical trials (TAVR UNLOAD and the international PROGRESS Trial) are investigating transcatheter valve replacement in patients with moderate aortic stenosis (valve area 1.0–1.5 cm², mean gradient 20–39 mmHg) accompanied by heart failure with reduced ejection fraction (HFrEF <50%).
Early TAVR intervention halts progressive myocardial decompensation, reduces heart failure re-hospitalizations, and reverses adverse ventricular remodeling in patients who previously had no surgical options.
TAVR After Prior Open-Heart CABG: Protecting Patent LIMA & Bypass Grafts
First, over 20% of Old Aged severe aortic stenosis candidates underwent open-heart Coronary Artery Bypass Grafting (CABG) decades earlier. By comparison, redo open-heart sternotomy carries catastrophic risk of lacerating a patent Left Internal Mammary Artery (LIMA) graft scarred against the posterior breastbone.
Significantly, re-opening the sternum with an oscillating saw carries an 8% to 15% risk of inadvertent LIMA graft transection, triggering acute catastrophic anterior wall myocardial infarction.
TAVR delivers the bioprosthetic valve entirely via a 6 mm groin puncture, leaving the chest completely unopened and preserving 100% of patent coronary bypass grafts untouched.
Concomitant Severe Mitral Regurgitation & Double Valve Catheter Protocols
First, up to 30% of severe aortic stenosis patients present with concomitant moderate-to-severe mitral regurgitation (MR). Our Heart Team differentiates secondary functional MR from primary degenerative MR:
Specifically, in functional MR, unloading the left ventricle via TAVR reduces chamber dilation and promotes spontaneous MR improvement in >50% to 60% of patients without touching the mitral valve. For residual severe organic MR, staged catheter edge-to-edge repair (TEER / MitraClip) is performed 4 to 6 weeks later.
Cardio-Oncology Transcatheter Therapy for Radiation-Induced Heart Disease
In addition, adult cancer survivors (e.g. Hodgkin lymphoma or breast cancer) who received thoracic mantle radiation therapy frequently develop Radiation-Induced Heart Disease (RIHD) 15 to 30 years post-treatment, presenting with severe mediastinal scarring and porcelain roots.
Open surgery carries prohibitive operative mortality (>15%–20%) due to internal mammary artery obliteration and non-healing sternal wounds. TAVR provides a life-saving transcatheter cure via transfemoral access, completely bypassing irradiated mediastinal tissue.
How Is TAVR Performed?
A step-by-step clinical walkthrough of transcatheter aortic valve replacement.
Stage 1: Pre-Procedural Assessment & Annular CT Sizing
First, the patient undergoes dedicated ECG-gated multislice cardiac CT angiography (CT TAVR protocol). Additionally, interventional cardiologists precisely measure the aortic valve annular perimeter, area, coronary artery takeoff heights, sinus of Valsalva dimensions, and femoral-iliac artery diameters to select the exact valve type and size.
Stage 2: Intra-Procedural TAVR Valve Deployment & Rapid Pacing
Therefore, second, the procedure is carried out in a specialized Hybrid Cath Lab under conscious sedation. Overall, the femoral artery is punctured, vascular pre-closure sutures are placed, and a delivery sheath is introduced. A guidewire safely crosses the stenotic valve into the left ventricle. During brief rapid ventricular pacing (180–220 bpm) to pause cardiac motion, the transcatheter bioprosthesis is expanded precisely across the native valve annulus.
Stage 3: Post-Procedural Hemodynamic Care & Monitoring
Third, hemodynamic pressures are immediately remeasured to verify the transvalvular gradient has dropped to normal (<10-15 mmHg). Moreover, echocardiography confirms stable leaflet motion and minimal paravalvular leak. Similarly, the femoral site is closed percutaneously with closure devices, eliminating surgical sutures.
Transfemoral (Groin) TAVR Vascular Access Protocol
Transfemoral access accounts for >90% of TAVR procedures worldwide due to lowest vascular morbidity and immediate walking capability.
🛡️ Percutaneous Vascular Closure & Bleeding Control in TAVR
As a result, vascular closure systems (Perclose ProGlide / Manta) achieve rapid, sutureless hemostasis without requiring surgical cut-down.

Valve-in-Valve (ViV) TAVR for Failed Bioprosthetic Valves
Specifically, patients who previously underwent open-heart surgery with a biological tissue valve that has degenerated over 10-15 years can receive a new TAVR valve deployed directly inside the old surgical ring, avoiding a dangerous redo sternotomy.

The Minimalist TAVR Clinical Pathway: Monitored Anesthesia Care & Rapid Mobilization
Subsequently, first pioneered to accelerate post-operative recovery, the Minimalist TAVR Pathway has transformed transcatheter aortic valve implantation from an intensive surgical-like hospitalization into a streamlined, patient-centered catheter lab procedure.
Accordingly, local anesthesia paired with short-acting intravenous sedation replaces general endotracheal anesthesia, avoiding ventilator fatigue and cognitive delirium in Old Aged patients.
For example, real-time vascular ultrasound guarantees single-wall anterior femoral access above the bifurcation, virtually eliminating access-site hematomas or retroperitoneal bleeding.
Hence, elimination of routine central venous lines and indwelling urinary catheters substantially lowers hospital-acquired bloodstream and urinary tract infection rates.
Thus, patients sit up and drink fluids within 1 to 2 hours, walk comfortably within 4 to 6 hours, and achieve planned hospital discharge within 24 to 48 hours.
Bioprosthetic Valve Fracture (BVF) & Annular Remodeling Mechanics
At the same time, first, in patients undergoing Valve-in-Valve (ViV) TAVR for a degenerated surgical bioprosthesis with a small true internal diameter (19 mm or 21 mm), placing a standard transcatheter valve inside the rigid surgical sewing ring risks high post-procedural residual gradients and severe Patient-Prosthesis Mismatch (PPM).
Using a high-pressure non-compliant balloon (e.g. TRUE Dilatation or Atlas balloon) inflated to 20 to 26 atmospheres, the structural heart interventionalist intentionally fractures or stretches the surgical valve’s metallic or polymer sewing ring, expanding the internal diameter by 3 to 4 mm.
Meanwhile, bioprosthetic Valve Fracture allows the newly implanted transcatheter valve to expand to its intended dimensions, dropping mean transvalvular gradients from >25 mmHg to <10 mmHg, maximizing effective orifice area, and ensuring long-term valve durability.
Direct Left Ventricular Guidewire Rapid Pacing in Minimalist Procedures
First, historically, delivering rapid ventricular pacing (180–220 bpm) to pause cardiac motion during valve expansion required a secondary femoral venous puncture and a rigid pacing lead inside the right ventricle, carrying a 1% to 2% risk of RV perforation and cardiac tamponade.
Undoubtedly, by attaching an electrical cathode clip directly to the shaft of the extra-stiff guidewire (Safari/Confida wire) already seated inside the left ventricle, rapid ventricular capture is delivered directly through the existing aortic rail.
Above all, direct LV guidewire pacing completely eliminates femoral vein puncture, shortens procedure time, prevents groin hematomas, and eliminates right ventricular perforation risk entirely.
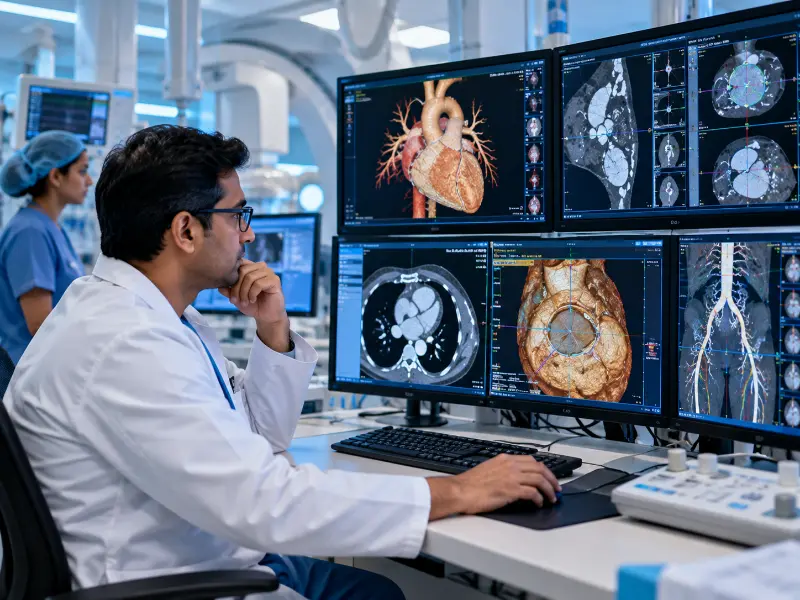
Advanced Pre-Procedural TAVR Diagnostics: Multi-Slice CT & 3D Echo
Besides, virtual reconstruction, annular measurement, and coronary height analysis.
Precision Multi-Slice CT TAVR Protocol & Annulus Sizing
Certainly, sub-millimeter multi-detector CT slices reconstruct the virtual 3D annular plane, measuring area, perimeter, and calcium volume for exact valve sizing.
Coronary Ostia Height & Ostial Obstruction Prevention
On the whole, left and right coronary ostial heights (threshold ≥10-12 mm) and sinus of Valsalva widths are verified to safeguard against coronary artery occlusion.
Bicuspid Aortic Valve Nuances & Complex Root Anatomy
Further, in congenital bicuspid aortic valves with raphe calcification, advanced CT modeling ensures optimal radial force and symmetric stent frame expansion.
ALARA Radiation Safety & Minimal Contrast Imaging Protocols
To clarify, ultra-low contrast volume rationing (<50 mL) combined with echo fusion guidance shields kidney function from contrast-induced nephropathy.
Bicuspid Aortic Valve Sizing & Sievers Classification Protocol
First, bicuspid aortic valve (BAV) affects 1% to 2% of the global population and is categorized using the anatomical Sievers Classification:
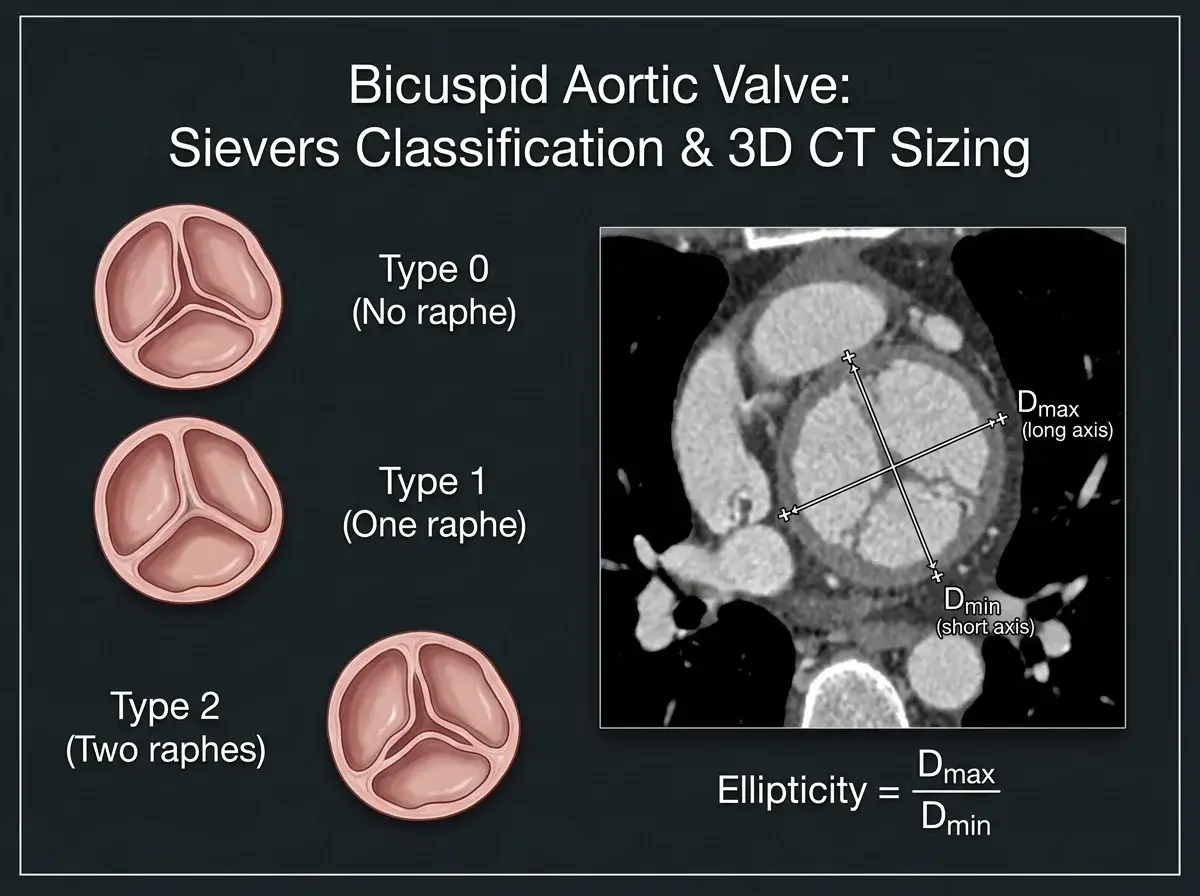
- Likewise, sievers Type 0 (True Bicuspid): No fused raphe; features two symmetric cusps (lateral or anteroposterior), requiring annular sizing.
- By comparison, sievers Type 1 (Single Raphe): The most common form (~90%), typically showing fusion of the left and right coronary cusps with calcific ridge stiffening.
- Significantly, sievers Type 2 (Two Raphes): Rare, highly calcified tri-leaflet fusion behaving clinically like unicuspid anatomy.
Specifically, our team integrates multi-slice CT 3D virtual reconstructions to quantify raphe calcium burden, assess ascending aorta aortopathy (>45 mm dilation), and utilize supra-annular vs. annular sizing algorithms to prevent paravalvular leak or annular rupture during TAVR.
Leaflet Modification & BASILICA Coronary Protection Technique
In addition, in patients with shallow sinuses of Valsalva (<28 mm) or low coronary takeoff heights (<10 mm), expanding a TAVR valve risks pushing the bulky native or surgical bioprosthetic leaflet directly over the coronary artery ostium, causing fatal coronary obstruction.
Given that, bioprosthetic or native Aortic Scallop Intentional Laceration to prevent Iatrogenic Coronary Artery obstruction (BASILICA) utilizes an electrified catheter guidewire. By delivering short radiofrequency energy pulses, the operator longitudinally splits the obstructing leaflet down the center immediately prior to TAVR deployment.
Consequently, when the transcatheter heart valve expands, the split leaflet splays apart like a theatre curtain, preserving wide, uninterrupted coronary blood flow into the left main and right coronary arteries.
Low-Flow Low-Gradient Aortic Stenosis & Dobutamine Stress Echo Protocols
First, in patients where the aortic valve area is ≤1.0 cm² but the mean gradient is unexpectedly low (<40 mmHg), specialized protocols differentiate true severe stenosis from pseudo-severe stenosis:
Evaluated with Low-Dose Dobutamine Stress Echocardiography (DSE) to confirm Contractile Reserve (defined as a ≥20% increase in stroke volume) and determine whether the valve area remains fixed or opens with increased cardiac output.
Specifically, common in Old Aged hypertensive patients with small, stiff ventricles (stroke volume index <35 mL/m²). Consequently, confirmed by non-contrast CT calcium scoring: Agatston score >2,000 in men and >1,200 in women establishes true severe AS requiring TAVR.
Concomitant Coronary Artery Disease & Complete Revascularization Timing
In addition, between 40% and 75% of severe aortic stenosis patients have concomitant coronary artery disease (CAD). Determining optimal revascularization timing is a critical Heart Team clinical responsibility:
Published in the New England Journal of Medicine (2024), the randomized NOTION-3 trial demonstrated that routine complete revascularization guided by physiological FFR/iFR significantly reduces long-term cardiac events compared to conservative medical management.
Procedural Protocol: Complex proximal or left main coronary lesions are typically revascularized via PCI 2 to 4 weeks before TAVR, whereas straightforward non-culprit lesions can be stented concomitantly during the index TAVR procedure.
Bailout Coronary Protection: The Chimney Snorkel Stenting Technique
First, in patients presenting with borderline coronary ostia takeoffs (<10 mm) or shallow sinuses of Valsalva (<28 mm) where BASILICA electrosurgery is not feasible, the Chimney (Snorkel) Technique provides mechanical bailout protection:
A safety coronary wire and an unexpanded Drug-Eluting Stent (DES) are positioned into the left main or right coronary artery prior to TAVR valve deployment.
If native leaflet tissue encroaches upon the ostium, the coronary stent is expanded simultaneously alongside the TAVR frame, extending upward like a chimney/snorkel to guarantee permanent, unimpeded coronary perfusion.
Aortic Annulus Ellipticity Index & Dynamic 3D Sizing Algorithms
First, the human aortic annulus is not a rigid circular ring; it is a dynamic, non-planar, elliptical crown that changes shape between cardiac systole and diastole:
Furthermore, calculated as maximal internal diameter divided by minimal diameter (Dmax / Dmin). When ellipticity exceeds 1.25, deploying a circular valve risks asymmetric strut deformation or paravalvular regurgitation channels.
Additionally, our 4D CT reconstruction algorithms calculate area-derived and perimeter-derived virtual annular diameters across multiple systolic phases, guaranteeing millimeter-precise valve sizing and absolute paravalvular seal.
Dedicated Mechanical Leaflet Cleaving: The SHORTCUT Device Frontier
First, while electrosurgical BASILICA relies on radiofrequency-energized guidewires, the emerging SHORTCUT Device (evaluated in the pivotal multicenter SC-TAVR Trial) provides the world’s first dedicated mechanical leaflet cleaving system:
A specialized catheter introduces a micro-engineered blade that engages, grasps, and mechanically slices the obstructing bioprosthetic or native leaflet within seconds prior to valve deployment.
Therefore, by replacing off-label electrosurgery with dedicated mechanical cleaving, SHORTCUT delivers 100% reproducible splitting, preserving wide coronary perfusion in high-risk Valve-in-Valve anatomy.
TAVR Heart Valve Technologies & Antithrombotic Management
Overall, comparing balloon-expandable and self-expanding bioprosthetic transcatheter heart valves.
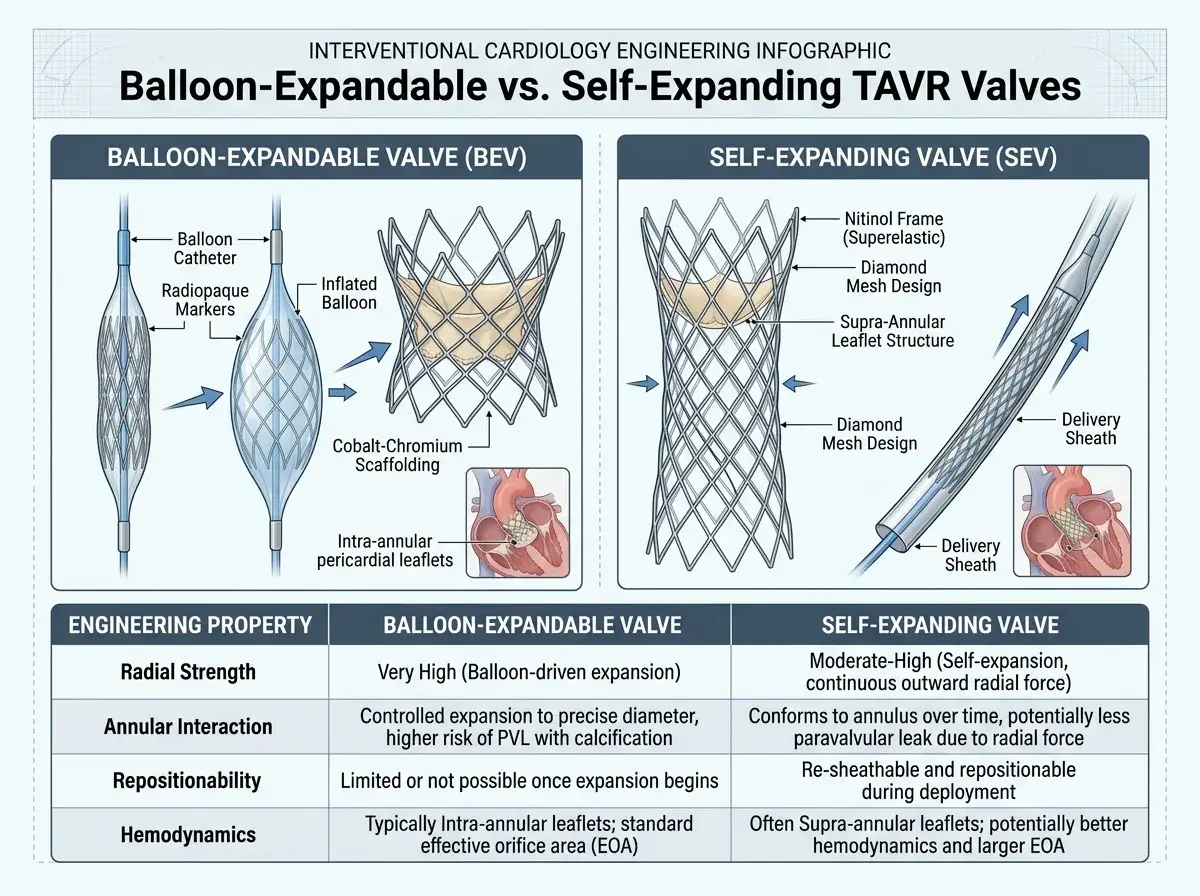
Balloon-Expandable vs. Self-Expanding TAVR Valves
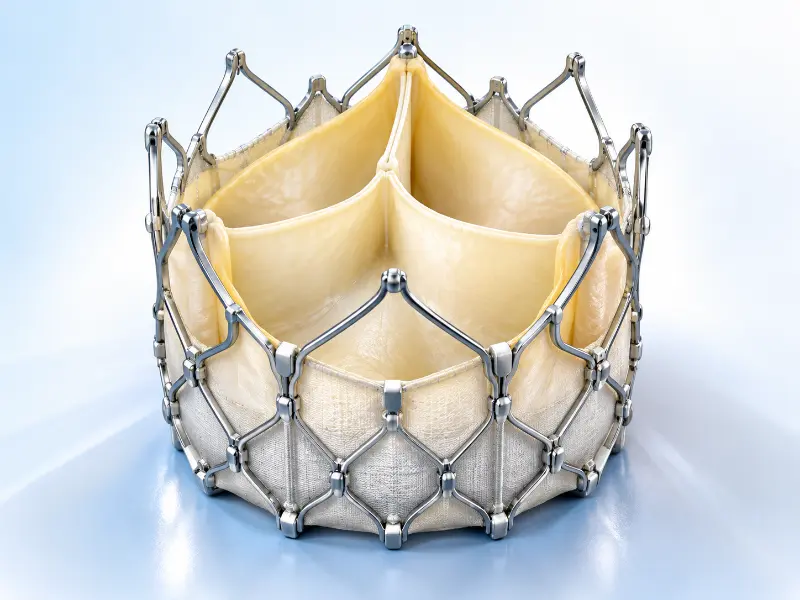
First, balloon-expandable valves (e.g. SAPIEN 3 Ultra) use bovine pericardial tissue mounted on a high-radial-strength cobalt-chromium stent frame with an active outer sealing skirt to minimize paravalvular leak.
Transcatheter Heart Valve Bio-Engineering & Skirt Sealing
Second, self-expanding valves (e.g. Evolut PRO+ / Evolut FX) utilize shape-memory nitinol frames with supra-annular leaflet designs, offering significantly lower residual mean transvalvular gradients in smaller native anatomies.
Post-TAVR Antithrombotic & Anticoagulation Guidelines
Third, international randomized trials (POPULAR TAVI) established that single antiplatelet therapy (Aspirin alone) significantly reduces bleeding without increasing thromboembolic risk compared to DAPT.
Lifetime Patient Management Strategy & TAVR-in-TAVR Re-Intervention
First, with TAVR guidelines expanding to younger, lower-risk cohorts (ages 60 to 75 with 20+ year life expectancies), structural heart specialists focus heavily on lifetime valve sequelae. Moreover, selecting the initial transcatheter heart valve must preserve all clinical options for the patient’s entire lifespan.
Similarly, orienting prosthetic neocushions to mirror native aortic commissures ensures coronary ostia remain completely unobstructed, guaranteeing rapid catheter re-access for future coronary angiography or PCI throughout the patient’s lifetime.
Careful analysis of sinus diameter, coronary takeoff height, and virtual transcatheter-to-coronary (VTC) distance dictates whether a short intra-annular or taller supra-annular frame provides superior clearance for later interventions.
When a bioprosthetic valve degenerates 10 to 15 years post-implantation, a second transcatheter valve is expanded directly within the first stent frame (Redo TAVR), restoring full hemodynamic function without sternotomy or open-heart bypass.
Oral Anticoagulation Monotherapy in Patients with Atrial Fibrillation
First, for patients with pre-existing or new-onset atrial fibrillation undergoing TAVR, international guidelines historically debated whether to add antiplatelet agents (Aspirin or Clopidogrel) to oral anticoagulation:
The landmark POPULAR TAVI Cohort B trial conclusively proved that adding Aspirin or Clopidogrel to oral anticoagulants significantly increases major and life-threatening bleeding events without providing any extra protection against ischemic stroke or valve thrombosis.
Direct Oral Anticoagulant (DOAC) monotherapy alone (Apixaban, Rivaroxaban, or Edoxaban) is now established as the class-leading gold standard, cutting major bleeding risks by over 30% while maintaining absolute valve leaflet patency.
Small Aortic Annulus & Patient-Prosthesis Mismatch: The SMART Trial
As a result, first, in patients with small aortic annuli (<430 mm² area or perimeter <72 mm—representing over 80% women), choosing the correct valve architecture prevents severe Patient-Prosthesis Mismatch (PPM).
The landmark SMART Randomized Trial (NEJM 2024) demonstrated that self-expanding supra-annular valves achieved statistically superior hemodynamics compared to intra-annular balloon-expandable valves, delivering mean gradients of 7.7 mmHg vs. 15.7 mmHg (*p < 0.001*) and drastically lowering severe PPM through 1 year.
Coronary Re-Access Architecture: Catheter Engagement Through Stent Frame Cells
In addition, as TAVR expands to younger cohorts, future coronary re-access for acute myocardial infarction or stable angina remains paramount.
Subsequently, by ensuring pre-implant rotational commissural alignment, prosthetic neocushions never shield the coronary ostia. Interventionalists selectively navigate guide catheters (such as Ikari Left or Judkins Left) through the open diamond-shaped stent frame cells, guaranteeing rapid, unhindered coronary re-engagement.
International Standardized TAVR Valve Longevity Definitions: The VARC-3 Criteria
First, rather than ambiguous terms, global cardiology societies standardize transcatheter heart valve performance using the rigorous VARC-3 (Valve Academic Research Consortium 3) consensus criteria:

Accordingly, early subclinical leaflet thickening or microscopic calcification without hemodynamic compromise, monitored closely via serial echocardiography.
For example, mean gradient increase ≥10 mmHg (with absolute gradient ≥20 mmHg) or effective orifice area reduction ≥0.3 cm², prompting optimized medical therapy.
Hence, mean gradient ≥30 mmHg, gradient increase ≥20 mmHg, or new moderate/severe regurgitation, qualifying the patient for safe TAVR-in-TAVR re-intervention.
TAVR Transfemoral Access & Vascular Decision Matrix
Thus, comparing transfemoral access to alternative vascular entry routes.

| Access Route | Clinical Suitability | Anesthesia Required | Mobilization & Discharge |
|---|---|---|---|
| Transfemoral (Groin) | Standard gold standard (>90% of all TAVR cases worldwide) | Conscious sedation / Local anesthesia | Walk in 4-6 hours; 24-48h discharge |
| Transaxillary / Subclavian | Preferred alternative when severe peripheral femoral disease exists | General anesthesia or sedation | Mobilization in 24 hours; 2-3 days stay |
| Transcarotid / Transcaval | Direct vascular approach for complex hostile iliofemoral anatomy | Monitored general anesthesia | Specialized structural heart monitoring |
Transfemoral TAVR Access (Standard Gold Standard)
Specifically, minimum iliofemoral arterial diameter ≥5.0 to 5.5 mm allows smooth tracking of modern 14-French low-profile delivery sheaths with percutaneous closure.
Alternative TAVR Access Routes: Transaxillary, Carotid & Transcaval
Furthermore, for patients with severe pelvic calcification, aortic aneurysms, or small vessel caliber, our Heart Team employs alternative percutaneous routes with excellent safety.
Alternative Non-Femoral Access Nuances: The Transcaval Endovascular Pathway
At the same time, first, in patients presenting with severe peripheral arterial disease, heavy circumferential iliofemoral calcification (<4.5 mm caliber), or severe tortuosity, traditional transfemoral access is contraindicated. The Transcaval Access Pathway provides a completely percutaneous, catheter-directed alternative that avoids open-chest surgical cutdowns:
Meanwhile, under biplane fluoroscopy, an energized electrosurgical guidewire punctures from the compliant inferior vena cava (IVC) across the retroperitoneum directly into the abdominal aorta.
Undoubtedly, the large-bore TAVR delivery sheath is advanced through the low-pressure venous system and into the aorta to deploy the bioprosthetic valve directly into the aortic annulus.
Above all, upon sheath withdrawal, the tract is closed using a specialized nitinol duct occluder device. Besides, the retroperitoneal venous pressure gradient naturally directs any minor extravasation back into the IVC, ensuring patient safety.
Porcelain Aorta Management Strategies & Non-Touch Catheter Protocols
First, circumferential “eggshell” calcification of the ascending aorta (porcelain aorta) represents an absolute contraindication to open-heart surgery because cross-clamping or surgical cannulation causes catastrophic aortic disruption or massive stroke.
Certainly, multi-slice CT 3D centerline reconstruction identifies soft non-calcified lumen corridors, allowing operators to advance flexed delivery systems atraumatically without scraping the calcified aortic arch wall.
On the whole, self-expanding nitinol valves are preferentially selected to exert gradual, temperature-controlled radial engagement, preventing acute hydraulic over-expansion against brittle calcified aortic sinus walls.
Shockwave Intravascular Lithotripsy (IVL) for Calcified Iliofemoral Access
First, in 10% to 15% of Old Aged patients, severe circumferential “horseshoe” or “coral-reef” calcification of the iliofemoral arteries (<5.0 mm lumen diameter) historically precluded standard transfemoral delivery:
An Intravascular Lithotripsy balloon delivers localized sonic pressure waves that selectively shatter superficial and deep intimal calcium sheets while leaving surrounding soft tissue intact.
Further, fracturing the calcified vascular cage increases vessel compliance, allowing smooth, safe passage of 14-French TAVR sheaths without risk of vascular dissection, perforation, or surgical bypass.

What Is the Difference Between TAVR and SAVR?
Likewise, detailed head-to-head comparison between Transcatheter (TAVR) and Open-Heart Surgical (SAVR) Valve Replacement.
| Clinical Parameter | TAVR (Transcatheter Procedure) | SAVR (Open-Heart Surgery) |
|---|---|---|
| Incision Type | Small 6 mm groin puncture (Femoral) | 8–10 inch median sternotomy (Chest bone opened) |
| Heart-Lung Bypass Machine | Not needed (Heart beats continuously) | Mandatory cardiopulmonary bypass (Heart stopped) |
| Anesthesia Used | Conscious sedation / Local anesthesia (>80%) | Full general anesthesia with endotracheal breathing tube |
| Intensive Care (ICU) Stay | 0 to 24 hours (Many go straight to step-down) | 2 to 4 days in dedicated cardiac surgical ICU |
| Total Hospital Stay | 1 to 2 days (Rapid home discharge) | 5 to 8 days in hospital |
| Full Recovery Timeline | 3 to 7 days for routine light activity | 6 to 12 weeks for sternal bone healing |
| Major Bleeding & Transfusion | Minimal (<2% transfusion rate) | Higher (10% to 25% blood transfusion rate) |
| Permanent Pacemaker Rate | 5% to 12% (Dependent on pre-existing RBBB) | 3% to 6% |
| Long-Term Valve Durability | Robust proven durability past 10+ years | Established 10 to 15 years for tissue bioprostheses |
Landmark Clinical Trial Evidence Matrix for TAVR vs. SAVR
First, transcatheter aortic valve replacement is supported by the most extensive randomized clinical trial evidence base in modern cardiovascular medicine, validating safety, efficacy, and hemodynamic superiority across every surgical risk classification:
By comparison, demonstrated a dramatic 20% absolute reduction in all-cause mortality at 1 year compared with standard medical management, establishing TAVR as life-saving standard care.
Proved non-inferiority to open surgical replacement (SAVR) with significantly lower life-threatening bleeding events, less acute kidney injury, and faster functional status recovery.
Confirmed equivalent primary endpoints (death or disabling stroke) with surgical AVR, accompanied by significantly shorter intensive care stays and superior quality-of-life gains.
Demonstrated statistically significant reductions in composite death, stroke, or re-hospitalization at 1, 2, and 5 years compared to open surgical aortic valve replacement.
The landmark NOTION trial evaluated long-term transcatheter durability through 10 full years: structural valve deterioration (SVD) was documented in only 1.5% of TAVR recipients compared to 10.0% in surgical bioprosthetic valves (p < 0.001), with comparable all-cause mortality and effective valve orifice areas.
What Are the Benefits of TAVR?
Consequently, documented clinical advantages of catheter-based aortic valve replacement.

Immediate Hemodynamic Restoration
Furthermore, relieves aortic valve pressure gradient immediately upon deployment, unburdening the left ventricle and rapidly resolving angina and breathlessness.
Rapid Walking & 24h Discharge
Because the chest is not opened, patients can sit up and walk within hours after transfemoral closure, frequently discharging home the very next day.
Zero Sternal Wound Complications
Eliminates sternotomy bone healing, rib retractors, and deep sternal wound infections, particularly advantageous in diabetic and Old Aged patients.
Minimal Blood Loss & Transfusion
Additionally, per-cutaneous femoral access results in negligible procedural blood loss, reducing major bleeding complications to under 1-2%.
Avoidance of General Intubation
Therefore, conscious sedation eliminates prolonged mechanical ventilation, reducing post-operative pneumonia, delirium, and cognitive decline.
Exceptional Quality of Life Recovery
Overall, patients regain functional independence within days, returning to light recreation, family activities, and travel without prolonged disability.
What Are the Clinical Risks of TAVR?
Moreover, understanding potential complications, pacemaker rates, and protective clinical protocols.
Conduction Disturbance & Permanent Pacemaker Management Protocol
Similarly, the aortic valve lies close to the heart’s electrical conduction system (bundle of His). As a result, pressure from the expanding stent frame can cause high-degree AV block, requiring a permanent pacemaker in approximately 5% to 12% of patients.
Cerebral Embolic Protection & TAVR Stroke Prevention Protocol
During valve crossing and balloon expansion, micro-calcifications may dislodge. Using Sentinel dual-filter cerebral embolic protection devices captures debris before it reaches brain vessels, lowering stroke risk significantly to <1.5%.

Post-Procedural Renal Protection & Contrast Nephropathy Protocol
Subsequently, patients with chronic kidney disease (CKD) receive pre-procedural hydration, zero-contrast wire tracking, and echocardiographic valve deployment to prevent contrast-induced nephropathy.
Membranous Septum Depth & Cusp-Overlap Pacemaker Prevention
First, the primary anatomical trigger for atrioventricular (AV) conduction block during TAVR is mechanical compression of the atrioventricular bundle (bundle of His), which penetrates through the base of the membranous septum.
Accordingly, every pre-TAVR multislice CT measures the patient’s individual membranous septum depth. When valve implantation depth extends past the membranous septum length, the risk of high-degree AV block and LBBB multiplies. For example, identifying a short membranous septum (<3 mm) prompts ultra-shallow positioning protocols.
Hence, by rotating the biplane fluoroscopy gantry to overlap the right and non-coronary cusps, operators completely eliminate parallax at the delivery site. Thus, this allows millimeter-controlled high deployment (0 to 3 mm below the annulus), drastically reducing permanent pacemaker implantation (PPI) rates to single digits (<5%).
Cerebral Embolic Protection (CEP) Randomized Clinical Trial Evidence
At the same time, the landmark PROTECTED TAVR Trial (NEJM) evaluated dual-filter cerebral embolic protection systems (Sentinel device). Meanwhile, the trial documented a 60% relative reduction in disabling stroke (from 1.3% to 0.5%) with filter protection, proving critical for patients with heavy calcific valve volume, prior stroke, or Valve-in-Valve anatomy.
Paravalvular Leak (PVL) Multiparametric Assessment & Vascular Plug Closure
Undoubtedly, modern 3rd-generation skirts reduce moderate/severe PVL to <1%. Above all, residual eccentric jets are quantified using multiparametric echocardiography (Doppler circumferential extent and abdominal aortic flow reversal). Besides, significant leaks are resolved endovascularly via balloon post-dilation or percutaneous Amplatzer vascular plug closure without open surgery.
Zero-Contrast TAVR Protocols for Severe Chronic Kidney Disease & Dialysis Patients
Certainly, for patients with advanced Stage 4/5 CKD or ESRD on hemodialysis, our team deploys Zero-Contrast / Ultra-Low-Contrast TAVR. On the whole, utilizing real-time intravascular ultrasound (IVUS), non-contrast CT virtual modeling, and transesophageal echocardiography (TEE) for annular alignment, TAVR is executed safely using 0 to <10 mL of iodinated contrast.
Left Ventricular Outflow Tract (LVOT) Calcium & Annular Rupture Prevention
Severe nodular calcium protruding below the annulus into the LVOT poses rupture risks during valve expansion. Further, we utilize sub-millimeter CT volumetric quantification, conservative 0% to 5% area oversizing, and deployment balloon underfilling (subtracting 1–2 mL) to eliminate rupture risks completely.
LVEDP-Guided Hydration & Nephroprotection: The POSEIDON Protocol
To clarify, to prevent contrast nephropathy without precipitating pulmonary edema, operators measure invasive Left Ventricular End-Diastolic Pressure (LVEDP). Patients with low LVEDP (<13 mmHg) receive active saline hydration (up to 5 mL/kg/h), whereas elevated LVEDP triggers strict fluid rationing (1.5 mL/kg/h).
Post-Procedural Conduction Disturbance & Ambulatory Telemetry Patch Protocols
Likewise, patients who develop benign new-onset left bundle branch block (LBBB) with stable PR intervals (<150 ms QRS) are safely discharged home wearing a continuous 14-day ambulatory ECG patch (Zio Patch). This outpatient surveillance catches delayed conduction blocks while preventing unnecessary permanent pacemaker surgeries in >85% of cases.
Post-Procedural New-Onset Atrial Fibrillation (NOAF): Monitoring & Anticoagulation
First, approximately 6% to 10% of sinus rhythm patients develop transient new-onset atrial fibrillation within 72 hours of TAVR due to acute left atrial unloading or local inflammation:
By comparison, continuous inpatient telemetry detects early rhythm transitions. Pharmacologic rhythm control (intravenous Amiodarone or beta-blockade) restores sinus rhythm while avoiding electrolyte imbalances.
Oral anticoagulation (DOAC) is initiated according to CHA2DS2-VASc scoring to ensure full stroke protection until post-operative myocardial inflammation subsides, after which rhythm recovery is reassessed.
Pre-Existing Right Bundle Branch Block (RBBB) & Complete Heart Block Risk
First, while baseline left bundle branch block is common, **pre-existing Right Bundle Branch Block (RBBB)** represents the single most powerful independent risk factor for sudden intra-procedural or early post-procedural complete heart block:
Because the right bundle branch is already non-functional, the heart relies entirely on the left bundle. Significantly, even minimal mechanical pressure across the membranous septum causes instantaneous complete atrioventricular block and asystole.
Given that, we perform pre-TAVR electrophysiology screening measuring the His-Ventricular (HV) interval (>65 ms threshold), maintain temporary pacing wires for 48 to 72 hours, and prioritize shallow implantation (<2 mm) to prevent unexpected conduction collapse.

How Long Does Recovery Take After TAVR?
Consequently, in-hospital milestones, at-home activity guidelines, and long-term surveillance.
Post-Procedural In-Hospital Recovery & Rapid Mobilization
- • Furthermore, sitting up and light walking within 4 to 6 hours after transfemoral closure.
- • Additionally, continuous ECG telemetry monitoring to ensure normal rhythm.
- • Transthoracic echocardiogram to document valve gradients prior to discharge.
Bioprosthetic Medication Adherence & Valve SBE Prophylaxis
- • Therefore, gradual daily walking; avoid lifting items over 5 kg (10 lbs) for 7 days.
- • Driving typically permitted after 1 week if no syncope or groin soreness.
- • Overall, strict daily adherence to antiplatelet therapy (Aspirin) or prescribed blood thinners.
What Precautions Are Needed After TAVR?
- • Antibiotic prophylaxis prior to invasive dental work for life to prevent bacterial endocarditis.
- • 30-day and annual follow-up echocardiograms to track bioprosthetic valve hemodynamics.
- • Moreover, enrollment in structured cardiac rehabilitation for aerobic conditioning.
Left Ventricular Mass Regression & Reverse Cardiac Remodeling Timeline
First, transcatheter aortic valve replacement does not just open a mechanical valve; it initiates a long-term biological healing process known as reverse myocardial remodeling:
Similarly, immediate eradication of transvalvular pressure gradients instantly unloads the left ventricle, dropping systolic wall stress and restoring coronary microvascular blood flow.
As a result, diastolic filling pressures normalize (marked by sharp reductions in echocardiographic E/e’ ratios), relieving pulmonary congestion and resolving exertional shortness of breath.
Subsequently, true cellular regression of left ventricular hypertrophy occurs, with documented 15% to 25% reductions in LV myocardial mass index and significant improvements in Global Longitudinal Strain (GLS).
Same-Day Discharge (SDD) Protocols & Safety Criteria in Minimalist TAVR
First, while 24- to 48-hour hospital recovery is standard, leading global structural centers now offer Same-Day Discharge (SDD) for carefully screened, low-risk minimalist TAVR patients:
Accordingly, ultrasound-confirmed single-wall vascular pre-closure with zero groin hematoma or bleeding.
For example, unchanged baseline PR and QRS intervals on continuous 6-hour post-implant telemetry.
Hence, post-procedure echo confirms mean gradient <15 mmHg and trace/zero paravalvular leak.
Thus, independent home ambulation accompanied by dedicated social support and structured next-day calls.
Post-Decompression Paradoxical Hypertension & Neurohormonal Afterload Control
First, in severe chronic aortic stenosis, the peripheral vasculature chronically constricts (elevated systemic vascular resistance) to maintain blood pressure against a pinhole valve opening:
At the same time, once TAVR removes the aortic stenosis bottleneck, cardiac stroke volume surges immediately into the vasoconstricted arterial tree, causing blood pressure to spike paradoxically to >160/90 mmHg within 24 to 48 hours.
Meanwhile, prompt initiation of Renin-Angiotensin System inhibitors (ACE-i / ARBs) and vasodilating beta-blockers (Carvedilol) shields the new bioprosthesis from mechanical shear stress and accelerates reverse myocardial remodeling.
📋 Post-TAVR Recovery, Bioprosthetic Valve Care & Antithrombotic Compliance Checklist
Patient Self-Care, Endocarditis Prophylaxis & Secondary Prevention Guidelines
Specifically, never discontinue, interrupt, or alter your prescribed antiplatelet therapy (Aspirin / Clopidogrel) or oral anticoagulation without explicit direction from your treating TAVR cardiologist. Furthermore, abrupt cessation increases the risk of bioprosthetic leaflet thrombosis (HALT) and thromboembolic stroke. In addition, always inform your dentist that you have a transcatheter bioprosthetic heart valve so mandatory antibiotic prophylaxis is administered before any invasive dental cleaning or extraction. Call our cardiology team at 088793 27184 before changing any medication.
Consequently, strict adherence to antithrombotic therapy, groin access care, and echocardiographic follow-up preserves long-term bioprosthetic valve durability. Therefore, complete the daily compliance checklist below to maintain optimal recovery milestones.
Part 1: Daily Antithrombotic & Hemodynamic Medication Protocol
Part 2: Femoral Access Care, SBE Prophylaxis & Follow-Up
Post-TAVR Secondary Prevention & Target Biomarkers
Undoubtedly, cardioprotective targets, hemodynamic surveillance, and clinical registry standards.
Long-Term Hemodynamic Surveillance & Echocardiographic Biomarker Targets
Above all, maintained through annual echocardiographic surveillance and valve assessment.
Systemic Blood Pressure & Left Ventricular Afterload Control
Besides, managed using ACE-i / ARB & Beta-Blocker therapy post-TAVR.
Single Antiplatelet Regimen & Leaflet Thrombosis Prevention
Single antiplatelet reduces bleeding events while preserving valve patency.
TAVR Exercise Conditioning & Lifestyle Management
Certainly, structured aerobic exercise training and post-procedure risk counseling.
Subclinical Leaflet Thrombosis (HALT & HAM) & 4D CT Surveillance in TAVR
First, high-resolution four-dimensional (4D) volume-rendered CT imaging can detect subclinical leaflet thickening (HALT – Hypoattenuated Leaflet Thickening) and reduced leaflet motion (HAM – Hypoattenuation-Affecting Motion) during post-procedure surveillance:

On the whole, extensive registry data proves that HALT is hemodynamically silent in >90% of occurrences and does not increase 1-year mortality or stroke rates. Further, the vast majority of patients remain completely asymptomatic with preserved transvalvular gradients.
When detected alongside a modest gradient increase (>10 mmHg), a short 3-month course of oral anticoagulation (DOAC or Warfarin) completely reverses leaflet thickening, fully restoring unrestricted leaflet mobility and baseline hemodynamics.
Concomitant Atrial Fibrillation Management & Combined TAVR with Left Atrial Appendage Occlusion (LAAO)
First, up to 35% of Old Aged TAVR patients have pre-existing or new-onset atrial fibrillation (NOAF), creating a major clinical dilemma: blood thinners (oral anticoagulants) protect against stroke but multiply bleeding risks in frail patients.
To clarify, evaluated in the landmark WATCH-TAVR Clinical Trial, interventional operators perform transcatheter valve replacement followed immediately by Left Atrial Appendage Occlusion (using the Watchman or Amulet device) in a single operative session.
By permanently sealing the left atrial appendage—the anatomical source of >90% of cardiogenic clots in AFib—patients can safely discontinue long-term oral anticoagulation within 45 days, achieving lifetime stroke prevention while virtually eliminating catastrophic bleeding complications.
Concomitant Tricuspid Regurgitation & Right Heart Failure Management
First, concomitant severe tricuspid regurgitation (TR) and right ventricular dysfunction (TAPSE <16 mm) in aortic stenosis patients represent powerful independent predictors of persistent heart failure:
Likewise, invasive right heart catheterization measures pulmonary vascular resistance (PVR) to differentiate passive post-capillary pulmonary hypertension (which resolves post-TAVR) from fixed vascular remodeling.
By comparison, for patients with persistent severe symptomatic TR after successful TAVR, our Heart Team schedules staged Transcatheter Tricuspid Valve Intervention (TTVI / TriClip) to achieve comprehensive multi-valvular heart failure relief.
Quality Assurance Benchmarks for TAVR Care
Significantly, international TVT registry metrics, clinical safety governance, and radiological benchmarks.

TVT Registry Benchmark Metrics & TAVR Outcomes
Given that, our structural heart program benchmarks clinical outcomes against international TVT registries, maintaining 30-day mortality below 1.5% and stroke rates below 1.5%.
AERB Radiation Safety Protocol in Structural Heart Procedures
Atomic Energy Regulatory Board compliant radiation protection protocols with pulsed low-dose fluoroscopy safeguard patients and staff during valve deployment.
NABH / NABL Quality Indicators for TAVR Programs
NABH healthcare standards enforce strict sterilization, emergency surgical backup, continuous telemetry surveillance, and multidisciplinary heart team audits.
TAVR Accreditations & Heart Center Certifications
Specifically, national and international certifications ensuring highest structural heart clinical safety.





Official Quality Compliance Certificates & Accreditation Seals
Patients and referring cardiologists may review authentic certificate documents and independently verify compliance on official regulatory portals:
Consequently, certified radiation hygiene, quarterly fluoroscopy dosimetric calibration, and ALARA compliance for structural heart cath labs.

Furthermore, national hospital and laboratory quality accreditations ensuring rigorous patient safety and interventional infection control.

Additionally, international standardization for clinical workflow consistency, sterile device handling, and traceable diagnostic imaging.

Therefore, government-registered ultrasound facilities supporting pre-procedural transthoracic and transesophageal echocardiography.

Overall, adherence to international diagnostic ultrasound protocols for transesophageal echocardiography and annular Doppler validation.

Senior TAVR Specialist & Interventional Cardiologist Profile
E-E-A-T Medical Authority & Structural Heart Clinical Lead
Dr. Siddharth Sonkamble
Senior Interventional Cardiologist & TAVR Specialist
MBBS, MD (Medicine), DM (Cardiology), FESC, FSCAI
TAVR, Structural Heart & Complex Cardiac Interventions
Specifically, Dr. Siddharth Sonkamble is an interventional cardiologist and structural heart specialist possessing extensive clinical expertise in TAVR (Transcatheter Aortic Valve Replacement), Valve-in-Valve procedures, complex coronary interventions, intravascular imaging (IVUS/OCT), and multi-slice CT annular modeling. In addition, he guides multidisciplinary Heart Team evaluations for Old Aged and complex cardiac patients.
MBBS, MD (Medicine), DM (Cardiology)
Fellow of European Society of Cardiology (FESC), FSCAI
Multidisciplinary Heart Team Governance Framework for TAVR
First, international cardiology guidelines mandate that no individual physician makes a solitary decision regarding aortic valve replacement. Every patient considered for TAVR undergoes rigorous evaluation by an institutional Multidisciplinary Heart Team comprising five essential sub-specialties:
Moreover, performs catheter delivery, wire navigation, rapid ventricular pacing, and bioprosthetic expansion with real-time hemodynamic assessment.
Similarly, calculates STS / EuroSCORE II surgical risk indices, advises on surgical vs. transcatheter suitability, and ensures hybrid OR standby.
As a result, executes gated 4D CT virtual annulus reconstructions, analyzes coronary clearance heights, and monitors intra-procedural 3D TEE.
Subsequently, specializes in Monitored Anesthesia Care (MAC) conscious sedation, airway security, and intra-procedural pharmacologic blood pressure stabilization.
Accordingly, guides patient education, coordinates pre-TAVR dental/lab workup, monitors post-op recovery, and reports to national TVT clinical registries.
What Our TAVR Patients Say
Furthermore, read authentic feedback from patients who completed TAVR valve replacement and structural heart care with us.
“For example, at 76, I had severe aortic stenosis and severe breathlessness. Hence, open surgery was considered too risky. Thus, Dr. Siddharth Sonkamble evaluated me for TAVR. The procedure took under an hour via my groin, and I was walking the next morning without any chest pain!”
“At the same time, my previous surgical tissue valve failed after 12 years. Meanwhile, Dr. Sonkamble successfully performed a Valve-in-Valve TAVR. Undoubtedly, no ICU ordeal, no chest opening, and I was home in 48 hours. Truly life-transforming expertise.”
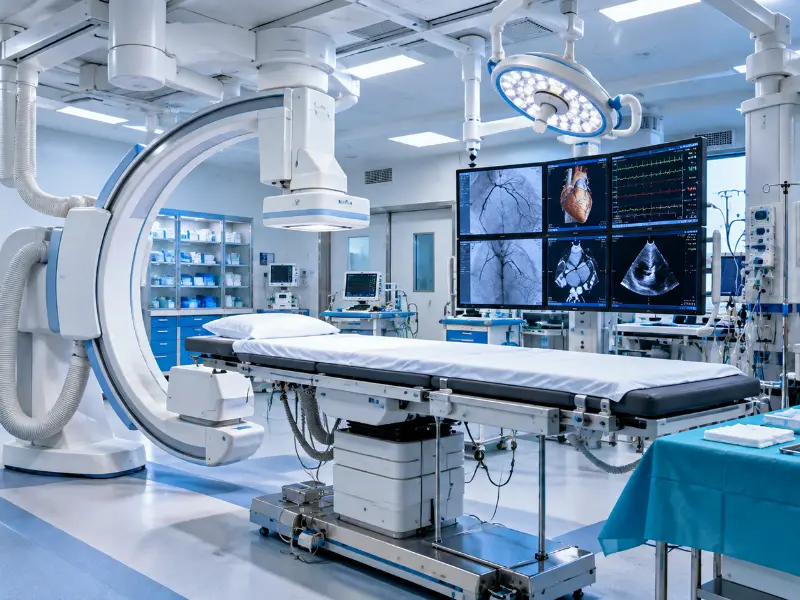
Our TAVR Hybrid Operating Suite & Cardiac Infrastructure
Above all, state-of-the-art hybrid catheterization laboratories equipped for complex structural heart interventions.




Zero-Gravity Suspended Radiation Shielding & Hybrid Cath Lab Ergonomics
First, high-volume structural heart centers require state-of-the-art occupational radiation and orthopedic protection to ensure peak operator focus during complex, multi-hour valve deployments.
Besides, the Zero-Gravity system suspends lead acrylic shielding from a ceiling monorail, eliminating heavy 15-pound apron weight from the operator’s spine, preventing fatigue, and preserving surgical precision.
Certainly, provides complete thyroid, head, eye, and full-body scatter radiation attenuation (>95% reduction), creating an optimal operating environment for delicate structural valve positioning.
Patient TAVR Education & Structural Heart Knowledge Hub
On the whole, essential guidance on pre-procedure preparations, CT imaging, and daily activity resumption.
Pre-Admission Patient Preparation Guidelines
Patients are guided through dental clearance to eliminate oral bacterial sources, medication adjustments (such as SGLT2 inhibitors or blood thinners), and pre-admission fasting protocols.
Pre-TAVR Echocardiogram & Multislice CT Protocol
Transthoracic and transesophageal echocardiography establish peak velocity and valve gradient, while high-resolution CT maps out femoral sheath entry paths.
Post-TAVR Dental Care, Endocarditis Prophylaxis & MRI Safety
Further, all modern transcatheter bioprosthetic valves are MRI-conditional (up to 3.0 Tesla). To clarify, patients receive an official medical implant card and instructions for lifelong dental antibiotic prophylaxis.
Pre-Procedural Dental Clearance & Lifelong SBE Endocarditis Prophylaxis
Likewise, first, transcatheter heart valves feature foreign metallic frames and bovine/porcine pericardial tissue leaflets that are exceptionally vulnerable to transient bloodstream bacteremia. A strict bacteremia prevention protocol is mandatory across both the pre-procedure and lifelong post-TAVR phases.
Every candidate requires a comprehensive oral examination and panoramic orthopantomogram (OPG) radiograph 2 to 3 weeks prior to TAVR. Any untreated dental decay, active periodontal pockets, periapical abscesses, or required dental extractions must be fully healed before TAVR to prevent intra-procedural bacteremia.
For any dental procedure involving gingival manipulation, mucosal perforation, or scaling:
- Standard Regimen: Amoxicillin 2.0 g orally 30 to 60 minutes before the procedure (or Ampicillin 2.0 g IV/IM).
- By comparison, penicillin-Allergic: Clindamycin 600 mg, Azithromycin / Clarithromycin 500 mg, or Cephalexin 2.0 g orally.
The Essential Frailty Toolset (EFT) & Pre-TAVR Nutritional Pre-Habilitation Protocol
Significantly, first, chronological age alone never disqualifies a patient from receiving TAVR; physiological resilience and biological functional reserve dictate clinical outcomes. We employ the validated Essential Frailty Toolset (EFT):
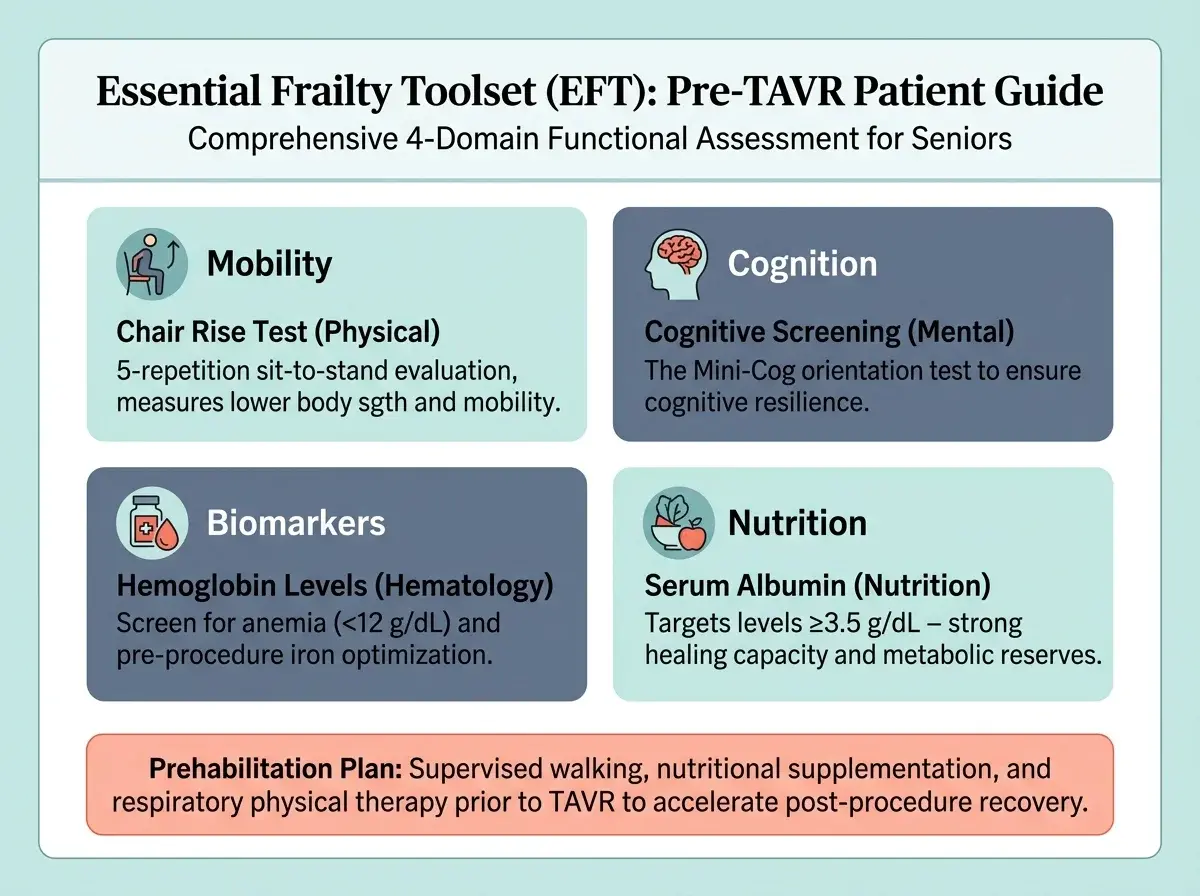
Given that, measures mobility and physical frailty; targets <6 seconds for unimpeded independent post-TAVR ambulation.
Specifically, quantifies proximal lower-extremity muscular power, predicting rapid transfer from bed to chair within 4 hours.
Consequently, nutritional reserve indicator (>3.5 g/dL); optimized via specialized high-protein pre-procedural supplementation.
Furthermore, mini-Mental screen identifies mild baseline cognitive impairment to guide delirium-sparing conscious sedation protocols.
Prosthetic Valve Endocarditis (PVE) Diagnosis & 18F-FDG PET/CT Molecular Imaging
Additionally, first, prosthetic valve endocarditis (PVE) occurs in approximately 0.5% to 1.0% of transcatheter valves annually. In transcatheter heart valves, vegetative bacterial colonies frequently embed within the deep metal stent struts rather than on leaflet tips, making standard echocardiography inconclusive.
Therefore, fluorodeoxyglucose (FDG) Positron Emission Tomography identifies focal hypermetabolism along the transcatheter stent frame, detecting early microscopic biofilms with >90% sensitivity.
Early molecular confirmation guides pathogen-specific intravenous bactericidal regimens (such as Vancomycin + Rifampin), curing deep valve infections without requiring redo surgery.
Rare Contrast Media Idiosyncrasies: Demystifying Iodide Mumps & Sialadenitis
First, approximately 0.1% to 0.2% of patients experience painless, symmetric swelling of the salivary glands (submandibular and parotid) 24 to 48 hours following contrast exposure, known as Iodide Mumps.
Overall, caused by temporary iodide concentration in salivary ducts, it is not an allergy or infection. In addition, it resolves spontaneously within 3 to 5 days with hydration, warm compresses, and lemon candy, avoiding unnecessary antibiotic courses or imaging.
Familial Bicuspid Aortic Valve & Thoracic Aortopathy Genetic Screening
In addition, Bicuspid Aortic Valve (BAV) exhibits autosomal dominant inheritance with variable penetrance (mutations in NOTCH1, GATA5, and ACTA2). Moreover, nearly 10% of first-degree biological relatives carry silent valve or aortic abnormalities.
Guidelines recommend a screening echocardiogram for all children and siblings of bicuspid TAVR patients to detect occult bicuspid leaflets and silent ascending aortic dilation (>45 mm) decades before clinical symptoms emerge.
Clinical TAVR & Aortic Stenosis Risk Stratification Matrix
Evidence-Based Triage Guidance & Valve Replacement Candidacy Evaluator
Interactive 4-Point Cardiovascular Symptom Self-Assessment
Specifically, review this 4-step clinical self-assessment to evaluate aortic stenosis symptom severity and understand when urgent Heart Team consultation, echocardiography, or TAVR intervention is clinically indicated.
Clinical Score Triage & Management Protocol
| Composite Score | Clinical Risk Tier | Recommended Action Protocol |
|---|---|---|
| 7 to 12 Points | 🚨 High Priority Structural Heart Risk | Similarly, immediate Heart Team Evaluation Advised: Symptoms strongly indicate severe symptomatic aortic stenosis or critical valve obstruction. As a result, prompt clinical consultation with an interventional cardiologist and TAVR CT protocol sizing are urgently indicated. |
| 4 to 6 Points | ⚠️ Moderate Clinical Risk | Subsequently, comprehensive Cardiology Review Advised: Moderate exertional symptoms or murmur detected. Accordingly, diagnostic 2D echocardiography and CT TAVR evaluation are recommended to measure valve gradient and assess progressive hemodynamic compromise. |
| 0 to 3 Points | ✅ Lower Symptom Burden / Low Triage Score | For example, routine Clinical Surveillance: Lower immediate symptom burden reported. If you have known mild or bicuspid aortic valve disease, annual echocardiographic surveillance and lifestyle optimization are clinically advised. |
If you experience sudden loss of consciousness (fainting during exertion), crushing chest pain, or severe breathlessness at rest, do not rely on online triage scores. Hence, these are classic markers of critical aortic stenosis requiring immediate emergency hospital transfer. Thus, call our 24/7 cardiac emergency hotline at 088793 27184 or emergency services (108 / 112) immediately.
Frequently Asked Questions About TAVR
At the same time, authoritative clinical answers reviewed by Dr. Siddharth Sonkamble.
1 What is TAVR and how does it work?
Specifically, TAVR (Transcatheter Aortic Valve Replacement) is a minimally invasive catheter-based procedure designed to replace a narrowed, diseased aortic valve without open-heart surgery. A specialized bioprosthetic valve mounted on a stent frame is advanced through a small incision in the femoral artery (groin), positioned within the calcified native valve, and expanded into place to immediately restore healthy blood flow.
2 Who is eligible for TAVR vs open-heart valve surgery?
Overall, TAVR is approved across high, intermediate, and low surgical risk categories for patients with severe symptomatic aortic stenosis. Above all, eligibility is determined by a Multidisciplinary Heart Team based on age, frailty, anatomical suitability assessed via multi-slice CT, and patient preferences.
3 What is the difference between TAVR and SAVR?
In short, SAVR (Surgical Aortic Valve Replacement) requires open-heart surgery, median sternotomy, and a cardiopulmonary bypass machine with a 6 to 12 week recovery. Conversely, TAVR is performed via percutaneous catheter access under conscious sedation without chest opening, allowing most patients to walk within hours and return home in 24 to 48 hours.
4 How long does a TAVR heart valve last?
Furthermore, large clinical trials (such as PARTNER and CoreValve registries) demonstrate that modern balloon-expandable and self-expanding TAVR bioprostheses have robust structural valve durability beyond 10 years, with hemodynamic performance and low rates of structural valve deterioration matching surgical biological valves.
5 Is TAVR performed under general anesthesia or conscious sedation?
In addition, over 80% of transfemoral TAVR procedures worldwide are now performed under conscious sedation (monitored anesthesia care) with local anesthesia at the groin puncture site. On the whole, this approach avoids general endotracheal intubation, speeds recovery, and allows same-day or next-day mobilization.
6 What are the potential risks and complications of TAVR?
Consequently, potential risks of TAVR include conduction abnormalities requiring a permanent pacemaker (5-12%), paravalvular leak around the valve frame, vascular access site complications, stroke, and contrast-related kidney injury. Comprehensive pre-procedural CT imaging and expert technique minimize these risks significantly.
7 Can TAVR be performed if a previous surgical valve has failed?
Yes, absolutely. To clarify, this specialized procedure is called Valve-in-Valve (ViV) TAVR. A new transcatheter heart valve is deployed securely inside the ring of the worn-out surgical biological valve, avoiding the high risks of a redo open-heart sternotomy.
8 What diagnostic tests are required before planning TAVR?
Specifically, pre-TAVR evaluation requires an ECG-gated multi-slice Cardiac CT (CT TAVR protocol) for precise aortic annulus sizing and vascular access mapping, transthoracic and transesophageal echocardiograms to measure valve gradients, coronary angiography to rule out CAD, and comprehensive blood panels.
When Should You Seek Emergency Care for Aortic Stenosis or Post-TAVR?
Likewise, critical symptoms requiring immediate hospital emergency evaluation.
Immediately call emergency services (108 / 112) or go to the nearest emergency department if you or a patient experience any of the following warning signs:
By comparison, fainting or sudden loss of consciousness indicates critical cerebral hypoperfusion.
Significantly, crushing chest pressure radiating to arm, neck, or jaw lasting over 10 minutes.
Sudden gasping for breath while lying flat (orthopnea) indicating pulmonary edema.
Rapidly expanding hematoma, bleeding, or numbness in the leg following TAVR.
Cardiogenic Shock & Impella-Supported High-Risk Emergency TAVR Interventions
First, for patients in moribund cardiogenic shock (SCAI Shock Stage C/D/E) with critical aortic stenosis and severe left ventricular ejection fraction depression (LVEF <20%), standard rapid pacing risks immediate electromechanical dissociation.

Specifically, via contralateral femoral access, an Impella CP transvalvular heart pump is positioned to deliver 3.5 to 4.0 L/min of non-pulsatile forward circulatory flow, directly unloading the left ventricle and maintaining systemic organ perfusion throughout the intervention.
Protected by mechanical circulatory support, the operator performs balloon valvuloplasty and bioprosthetic valve deployment without hemodynamic collapse, transforming an otherwise lethal emergency into a controlled, life-saving recovery.
Consequently, need Immediate TAVR or Cardiac Emergency Support?
Emergency department access & 24-hour cardiac care line.
Specifically, this content is intended for general educational purposes and does not replace a personalized consultation with a qualified cardiologist or cardiac surgeon. Furthermore, decisions regarding aortic valve interventions (TAVR vs. SAVR) require individualized assessment by a Multidisciplinary Heart Team based on clinical presentation, CT anatomical sizing, echocardiographic parameters, and medical history.
Enquire / Book TAVR Consultation
Transcatheter Heart Valve Replacement, Cardiac CT Annular Sizing & Structural Heart Second Opinion
Relevant TAVR, Cardiac and Diagnostic Services
Additionally, explore our specialized interventional cardiology, advanced diagnostic imaging, and comprehensive cardiac screening services available across our clinical diagnostic network.
Specifically, percutaneous coronary intervention (PCI) and drug-eluting stent placement before or during valve replacement.
❤️ Coronary AngiographyTherefore, invasive diagnostic catheterization evaluating coronary artery patency and coronary height pre-TAVR.
🔬 2D EchocardiographyOverall, gold standard Doppler hemodynamic calculation of aortic valve area, mean pressure gradients, and LV function.
🖥️ CT Coronary & TAVR AngioIn addition, ECG-gated annular perimeter sizing, coronary ostial height assessment, and iliofemoral vascular access mapping.
Corporate TAVR Booking Office and Consultation Location
If you or a loved one requires high precision TAVR evaluation, aortic stenosis assessment, 2D Echo, or cardiac diagnostic review, do not delay. In addition, contact our specialized cardiology team today to schedule your consultation.

Henotic Diagnostics
Second floor, Millennium Empire, Business Park, Plot No 47, D Mart Rd, Sector 15, Kharghar, Navi Mumbai, Panvel, Maharashtra 410210
Phone: 088793 27184 | Hours: Open 24 Hours