Cardiac Catheterization: Comprehensive Heart & Coronary Evaluation
Specifically, a clinical deep-dive into diagnostic cardiac catheterization, coronary angiography, hemodynamic intracardiac pressure analysis, patient preparation protocols, risk stratifications, and aftercare recovery.
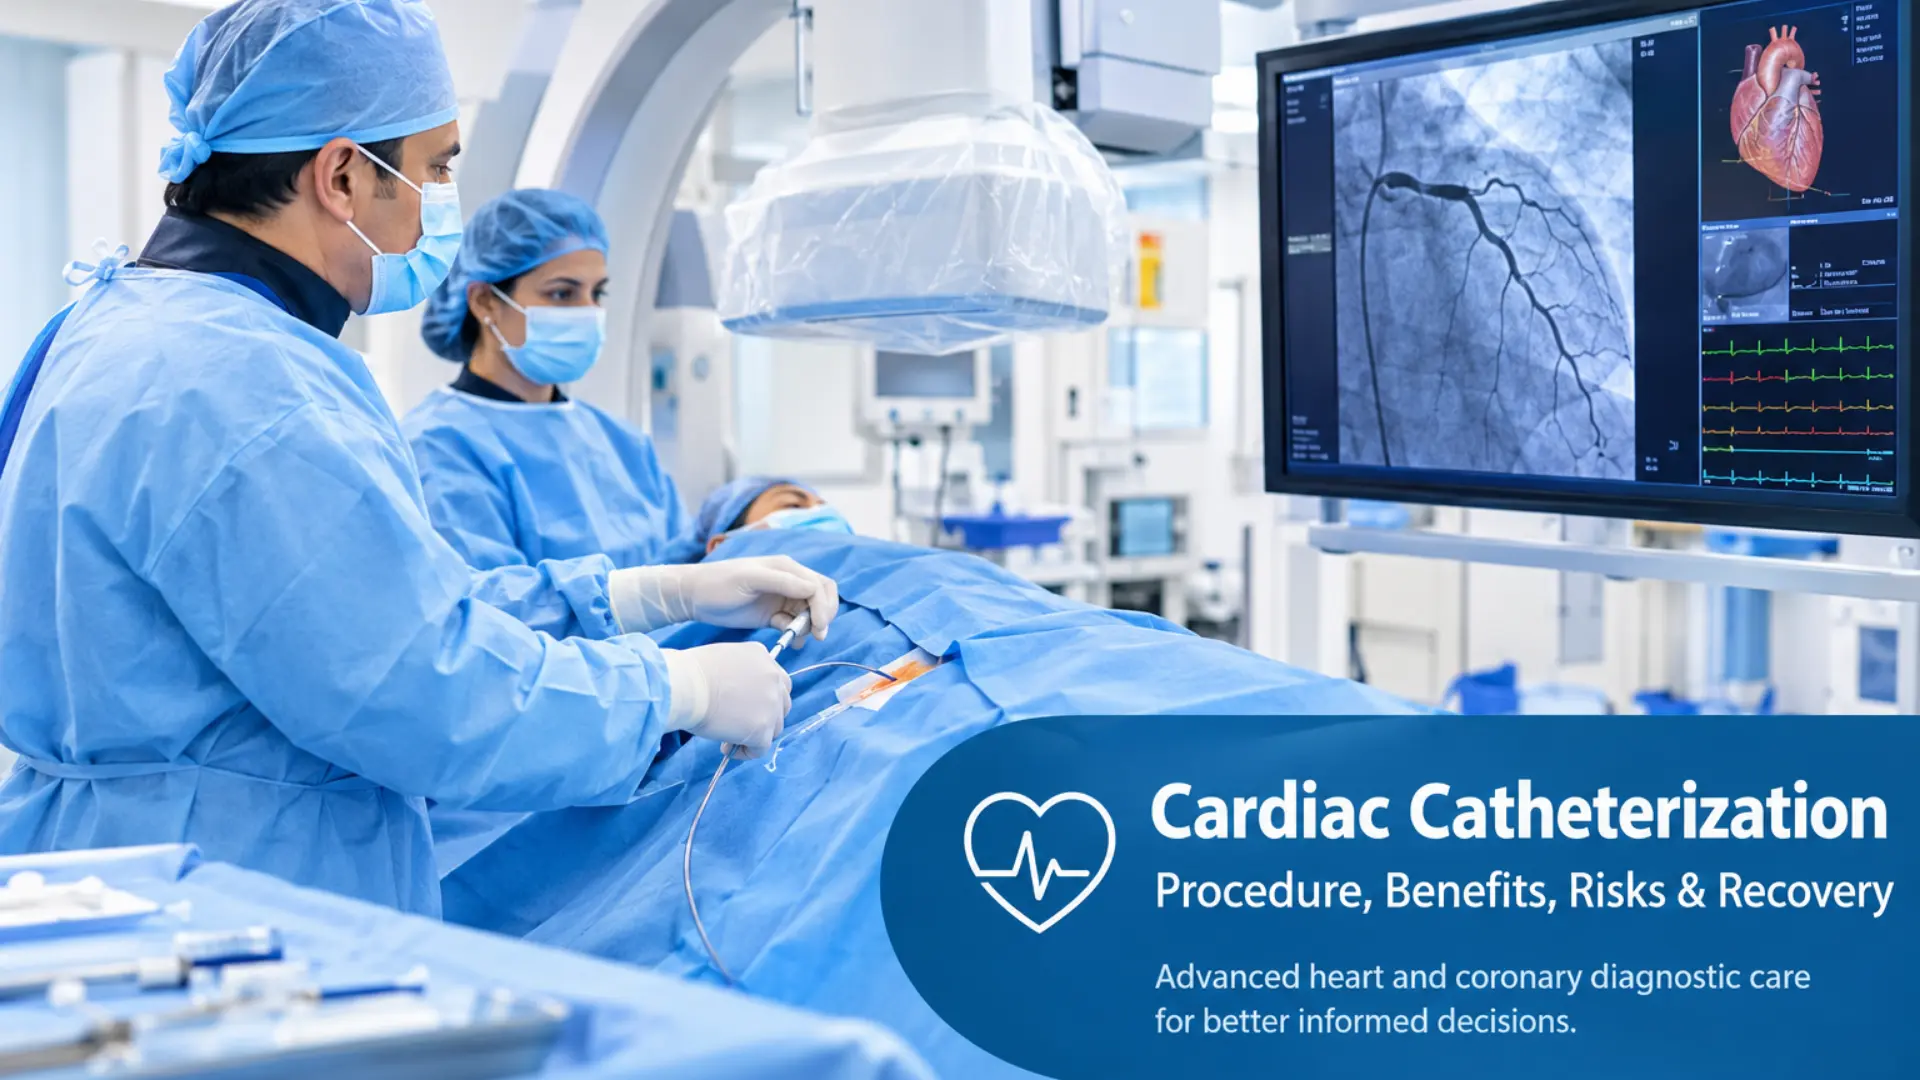
Additionally, radial / Femoral Route: Micro-catheter inserted via wrist (transradial) or groin under live fluoroscopic guidance with minimal recovery downtime.
Consequently, diagnosis & Stenting: Visualizes arterial stenosis with immediate capability for balloon angioplasty and drug-eluting stent (DES) deployment.
Moreover, chamber Pressures: Directly records intracardiac chamber pressures, cardiac output, and oxygen gradients to evaluate complex valve disease.
Furthermore, Cardiac Catheterization Guide: 18 Evidence-Based Clinical Chapters
Therefore, select any chapter below to navigate directly to detailed clinical protocols, procedure explanations, preparation guidelines, diagnostic comparisons, accreditations, specialist consultations, and related diagnostic services.
Specifically, Diagnostic, Procedural & Recovery Chapters
Additionally, Cardiac Catheterization: Comprehensive Heart & Coronary Evaluation
In particular, Cardiac catheterization is a specialized medical procedure used to evaluate heart function, assess blood flow through the coronary arteries, and measure pressures inside the heart. For example, it helps cardiologists investigate certain cardiovascular conditions and determine appropriate treatment options.
As a result, at Henotic Diagnostics, patient education about cardiac catheterization focuses on understanding the procedure, its clinical purpose, preparation requirements, potential risks, and recovery considerations. In addition, the decision to perform this procedure should be based on an individual’s symptoms, medical history, diagnostic findings, and the treating cardiologist’s recommendations.
Additionally, Understand Your Heart. Specifically, Explore Your Diagnostic Options.
Notably, contact the appropriate cardiac care team to discuss whether cardiac catheterization is suitable for your clinical needs.

Consequently, Specifically, Dr. Siddharth Sonkamble MD, DM (Cardiology)
Dr. Accordingly, siddharth Sonkamble is an experienced Interventional Cardiologist specializing in complex coronary angiography, intracardiac pressure dynamics, and catheter-based cardiovascular therapeutics. Similarly, he oversees the clinical accuracy and patient safety protocols published by Henotic Diagnostics.
Specifically, AHA & ACC Guidelines Aligned
In contrast, all clinical indications and catheterization thresholds follow Class I & IIa consensus guidelines established by the American College of Cardiology.
Furthermore, AERB Low-Dose Radiation Survey
Ultimately, fluoroscopy equipment operates under valid AERB radiation registrations with real-time Dose Area Product (DAP) tracking to safeguard patient tissue.
Additionally, ISO 13485 & NABH Single-Use Mandate
Overall, zero reuse policy: 100% of vascular sheaths, micro-puncture needles, and pre-formed diagnostic catheters are individually barcode-tracked and single-use.
Consequently, What Is Cardiac Catheterization?
Notably, Cardiac catheterization is a minimally invasive procedure in which a healthcare professional guides a thin, flexible tube called a catheter through a blood vessel toward the heart. Accordingly, the catheter is commonly introduced through an artery or vein in the wrist or groin, depending on the purpose of the examination.
Similarly, during the procedure, clinicians may use X-ray imaging, contrast material, and specialized instruments to examine cardiovascular structures or obtain important physiological measurements.
In contrast, Cardiac catheterization can help evaluate coronary artery narrowing, certain heart valve conditions, congenital heart abnormalities, and abnormal pressures within the heart or pulmonary circulation. Ultimately, its exact role depends on the clinical indication.
Unlike a routine external examination, cardiac catheterization allows selected measurements and images to be obtained directly from within the cardiovascular system.
Therefore, Vascular Access Routes for Cardiac Catheterization: Transradial vs. Transfemoral
Overall, clinical decision metrics governing the vascular pathway selected for catheter advancement.
Therefore, Transradial Artery Route (Wrist)
- Specifically, Anatomy: Radial Artery (2.2–2.8 mm caliber)
- Furthermore, Puncture Needle: 20G/21G Micro-Puncture Kit
- Additionally, Bleeding Complication: < 0.1% Major Access Bleed
- Consequently, Post-Cath Mobility: Immediate upright sitting • Walk in 2 hrs
- Moreover, Primary Benefit: Patient comfort, zero groin exposure, same-day discharge
In Particular, Transfemoral Artery Route (Groin)
- Therefore, Anatomy: Common Femoral Artery (6.0–8.0 mm caliber)
- In particular, Puncture Needle: 18G Standard Arterial Needle
- Notably, Bleeding Complication: ~1.2%–1.8% Hematoma incidence
- In addition, Post-Cath Mobility: 4–6 hours strict flat supine bed rest
- Accordingly, Primary Indication: Tortuous radial loops, small-caliber arteries, large-bore PCI
In particular, Cardiac Catheterization Clinical Glossary & Jargon Decoder
Meanwhile, essential catheterization terms, hemodynamic metrics, and medical acronyms translated into plain clinical language.
Subsequently, narrowing or constriction of a coronary arterial lumen caused by progressive atheromatous plaque buildup, restricting oxygen delivery to the heart muscle.
Indeed, an expandable microscopic cobalt-chromium mesh scaffold coated with a time-released antiproliferative medication that permanently prevents scar tissue re-narrowing.
With this in mind, a precision pressure-wire measurement calculated across a blockage. To clarify, an FFR value ≤ 0.80 confirms blood flow starvation and indicates stenting benefit.
A transparent wrist compression cuff inflated with titrated air to secure complete radial artery hemostasis while maintaining continuous ulnar collateral circulation.
In fact, a low-risk radiopaque fluid formulated to match normal human serum osmolarity (~290 mOsm/kg), highlighting arteries in 4K X-ray without stressing kidney nephrons.
Specifically, direct catheter recording of intraventricular pressure at end-diastole, serving as a primary clinical marker for left heart compliance and heart failure staging.
Moreover, Why Is Cardiac Catheterization Performed?
Furthermore, a cardiologist may recommend cardiac catheterization when additional information is needed to diagnose a cardiovascular condition, assess its severity, or guide treatment.
In addition, Suspected Coronary Artery Disease & Cardiac Catheterization
Specifically, this procedure examines the coronary arteries when clinically indicated for critical narrowing or arterial obstructions.
Notably, Chest Pain Evaluation Through Cardiac Catheterization
Furthermore, interventional cardiologists investigate selected cases of unexplained or worsening suspected cardiac-related chest discomfort.
Similarly, Abnormal Cardiac Test Results Requiring Cardiac Catheterization
Additionally, this gold-standard study clarifies inconclusive or high-risk findings identified on stress testing, ECG, or echocardiography.
Ultimately, Heart Valve Assessment via Cardiac Catheterization
Moreover, hemodynamic catheterization accurately evaluates selected valve-related conditions and their physiological effects on intracardiac blood flow.
Overall, Heart Failure Evaluation via Cardiac Catheterization
Consequently, clinicians measure intracardiac pressures and investigate underlying myocardial causes in appropriate heart failure patients.
Meanwhile, Congenital Heart Disease & Diagnostic Cardiac Catheterization
In addition, specialized catheterization evaluates adult congenital heart defects, intracardiac shunts, and complex vascular anatomy.
Subsequently, Pulmonary Hypertension Assessment via Right Heart Catheterization
Simultaneously, right heart catheterization precisely records pulmonary capillary wedge pressures and pulmonary vascular resistance.
Indeed, Interventional Treatment Planning and Cardiac Catheterization
Ultimately, definitive angiographic mapping determines whether medical optimization, immediate balloon angioplasty, or bypass surgery is recommended.
Clearly, Coronary Stenosis Severity & Cardiac Catheterization Pathway
Additionally, during catheterization, the cardiologist measures the exact percentage of arterial lumen narrowing to determine whether medication, stenting, or bypass is indicated:
In Addition, Mild Atherosclerotic Plaque
Consequently, minimal resistance to resting or exertional coronary blood flow. Moreover, myocardial oxygen demand is fully met during strenuous exercise.
Therefore, specifically asymptomatic. Often detected incidentally during coronary CT angiography or routine executive screening.
In particular, guideline-Directed Medical Therapy (GDMT): High-intensity statin therapy (Atorvastatin/Rosuvastatin), lifestyle optimization, strict blood pressure control. For example, stenting is NOT indicated.
Notably, Moderate Luminal Narrowing
As a result, visual estimation alone is insufficient. In addition, lesion may or may not cause true physiological ischemia during hyperemia.
Notably, occasional exertional breathlessness or atypical angina during intense stair climbing or brisk walking.
Accordingly, pressure-Wire Guided Assessment: If FFR ≤ 0.80 or iFR ≤ 0.89, proceed to Drug-Eluting Stent (DES). Similarly, if FFR > 0.80, continue medical therapy safely without stenting.
Similarly, Severe Coronary Stenosis
In contrast, significant translesional pressure drop. Ultimately, marked impairment of myocardial blood flow reserve leading to downstream myocardial hypoxia.
Overall, predictable exertional angina (retrosternal heaviness), positive treadmill test (TMT >2mm ST depression), resting ECG changes.
Meanwhile, percutaneous Coronary Intervention (PCI): Ad-hoc balloon angioplasty and Drug-Eluting Stent (DES) deployment in the same sitting. Subsequently, if left main or complex multi-vessel disease, evaluate for CABG.
Ultimately, Acute STEMI or Chronic Total Occlusion
Indeed, complete cessation of blood delivery through the primary lumen. With this in mind, myocardial viability depends entirely on retrograde collateral vessels.
To clarify, acute: Severe crushing chest pain, diaphoresis, acute myocardial infarction (heart attack). In fact, chronic: Refractory angina, ischemic cardiomyopathy.
Specifically, emergency Primary PCI: Urgent catheterization within <90 minutes door-to-balloon time to reopen the culprit vessel, aspirate thrombus, and restore TIMI-3 perfusion.
Furthermore, note: Not every patient with chest pain or an abnormal cardiac test requires catheterization. Non-invasive investigations and the overall clinical picture help determine the most appropriate next step.
Therefore, Types of Cardiac Catheterization
Additionally, Cardiac catheterization encompasses several procedures. Consequently, the technique selected depends on the suspected condition and the information required.
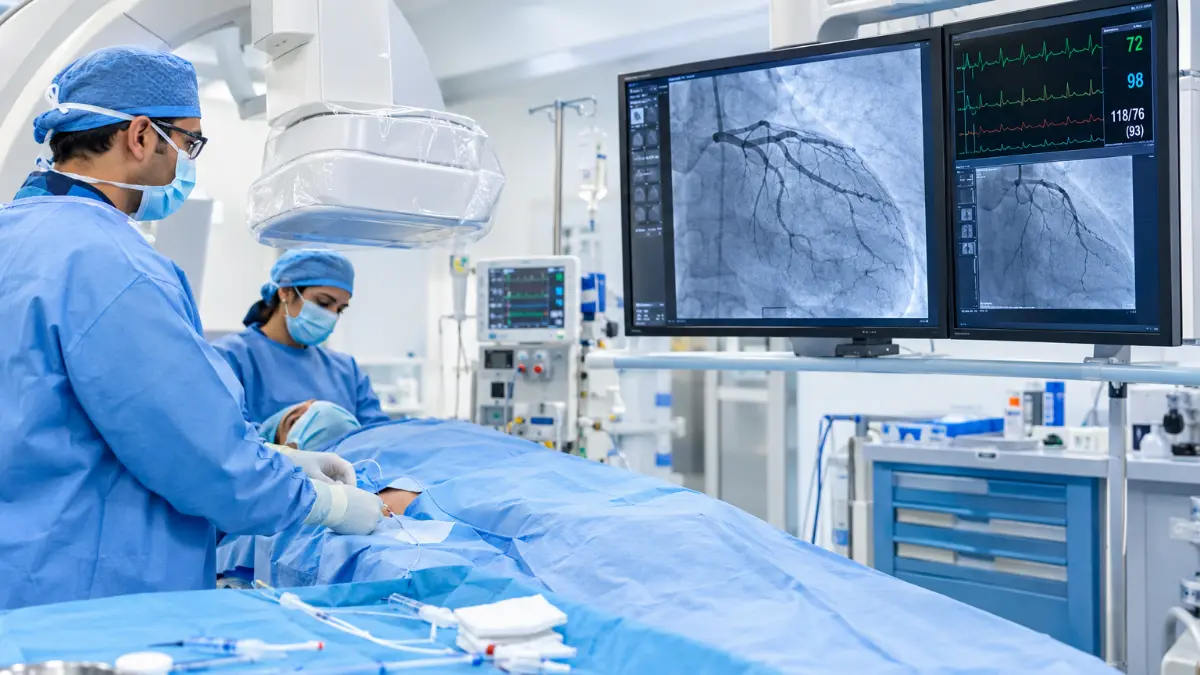
Generally, 1. Coronary Angiography
Moreover, Coronary angiography uses contrast material and X-ray imaging to visualize the coronary arteries. Therefore, it helps clinicians identify the location and extent of narrowing or blockage that may affect blood supply to the heart muscle. In particular, the findings assist cardiologists in evaluating medical management, angioplasty, stenting, or bypass surgery.
In fact, 2. Right Heart Catheterization
For example, right heart catheterization measures pressures in the right atrium, right ventricle, and pulmonary artery. It also evaluates cardiac output and haemodynamic parameters when assessing pulmonary hypertension, unexplained breathlessness, or complex heart failure.
As a result, 3. Left Heart Catheterization
As a result, left heart catheterization provides access to selected measurements within the left side of the heart. In addition, depending on the approach and clinical purpose, it helps evaluate left ventricular pressure, aortic pressure, or other aspects of cardiac function.
Accordingly, 4. Cardiac Catheterization With Coronary Intervention
Notably, in certain cases, diagnostic catheterization is followed by a therapeutic procedure. Accordingly, percutaneous coronary intervention (PCI) may involve balloon angioplasty and placement of a coronary stent to improve blood flow through a narrowed artery during the same session or scheduled separately.
Specifically, Intravascular Pressure Waveform Architecture in Cardiac Catheterization
Similarly, select a cardiovascular circuit below to review selective catheter engagement, baseline intracardiac pressure telemetry, and clinical diagnostic value.
Overall, Left Anterior Descending (LAD) & Circumflex (LCx) Arteries
In contrast, supplies over 65% of left ventricular myocardial blood mass (“The Widowmaker” territory). Ultimately, selective cannulation assesses epicardial stenoses, bifurcation lesions, and distal runoff.
Meanwhile, Right Coronary Artery (RCA) & Posterior Descending Artery (PDA)
Overall, courses in the right atrioventricular groove to supply the right atrium, right ventricle, sinus/AV nodes, and inferior diaphragmatic left ventricular wall in 85% of right-dominant hearts.
Subsequently, Left Ventriculography & End-Diastolic Pressure (LVEDP)
Meanwhile, the catheter traverses the aortic valve into the LV chamber. Subsequently, measures real-time intraventricular pressures and calculates global Ejection Fraction (LVEF %) via high-flow power injection.
Specifically, Right Heart Catheterization (Swan-Ganz Thermodilution)
Indeed, introduced via internal jugular or femoral vein into the pulmonary bed. With this in mind, obtains gold-standard hemodynamic pressures and measures thermodilution Cardiac Output to classify pulmonary hypertension.
Furthermore, From Diagnostic Cardiac Catheterization to Immediate Stenting: Ad-Hoc PCI
When an angiogram detects a critical stenosis (>70% arterial blockage), treatment can be performed immediately in the same 45-minute session without a second puncture or separate hospital stay.
Clearly, Diagnostic Cineangiography
To clarify, radiopaque dye reveals the exact coronary anatomy, bifurcations, and pinpoint location of the narrowed vessel segment.
Specifically, On-Table Assessment & Consent
In fact, the interventional cardiologist discusses lesion severity with the patient/family and initiates the pre-approved interventional protocol.
Furthermore, Guidewire & Stent Deployment
Specifically, a 0.014-inch microwire crosses the stenosis. Furthermore, a balloon pre-dilates the lesion, followed by precise deployment of a Drug-Eluting Stent (DES).
Finally, Flow Restoration & Closure
Additionally, final angiography confirms 100% TIMI-3 flow restoration. Consequently, the sheath is painlessly removed and a radial TR-Band compressor is applied.
In particular, How Does Cardiac Catheterization Work?
Moreover, the procedure is performed by a qualified clinical team in an appropriately equipped cardiac catheterization laboratory.
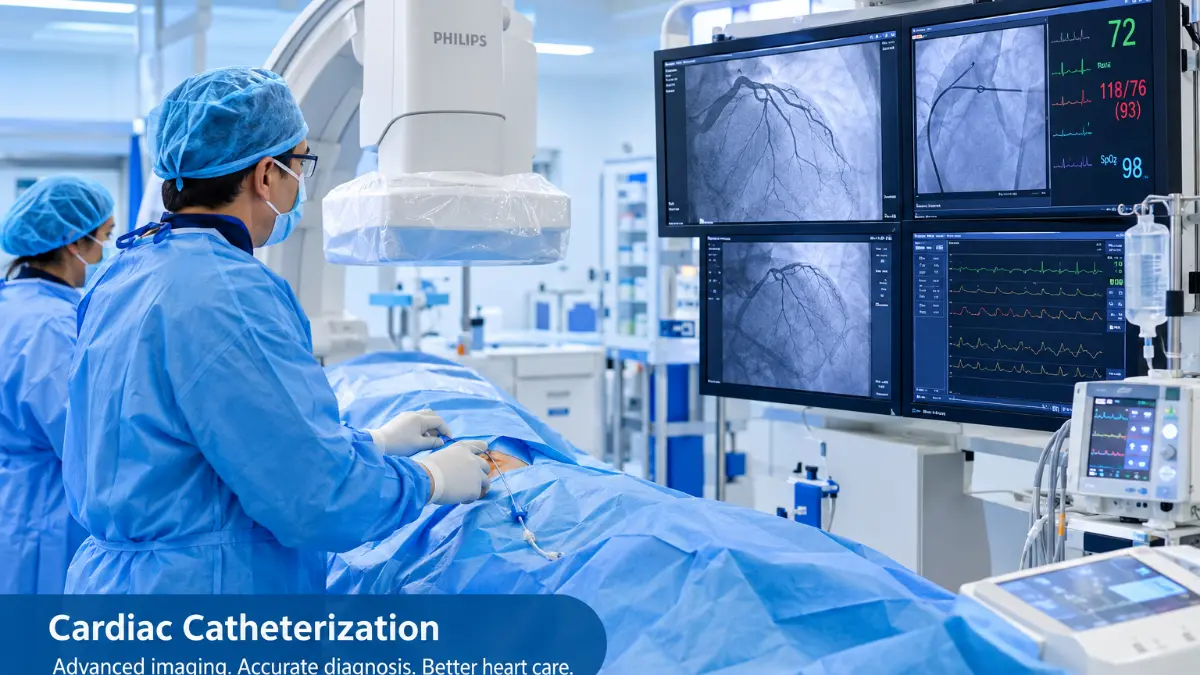
Consequently, Typical Procedural Timeline: ~30 to 45 Minutes
Therefore, chronological phase progression inside the sterile cardiac catheterization lab.
Additionally, Inside the Cardiac Catheterization Lab: Advanced Procedural Architecture
In particular, a specialized, high-technology medical environment engineered for sub-millimeter precision, patient comfort, and continuous hemodynamic telemetry:
Moreover, Flat-Panel Digital C-Arm Fluoroscopy
For example, a robotic C-arm rotates around the radiolucent carbon-fiber procedural bed to capture compound angulations (LAO Cranial, RAO Caudal) without shifting the patient. Emits ultra-low pulsed X-rays while producing crystal-clear high-definition 1024×1024 digital cineangiograms.
Therefore, Multichannel Hemodynamic Telemetry
As a result, fluid-filled pressure transducers continuously monitor intra-arterial and intracardiac pressure wave waveforms (Left Ventricular End-Diastolic Pressure, Aortic Root Pressure) alongside synchronized 12-lead ECG and continuous pulse oximetry.
Specifically, Automated Micro-Contrast Injector
Furthermore, microprocessor-controlled hydraulic injector dispenses radiopaque contrast media at precise flow rates (2.5–4.0 mL/sec) and pressures. Notably, automatically caps total dye volume (<60 mL) to protect renal filtration and prevent contrast-induced nephropathy.
In Addition, Intravascular Imaging & FFR Console
Accordingly, direct integration with Fractional Flow Reserve (FFR/iFR) optical pressure wires and Intravascular Ultrasound (IVUS) to visualize atheromatous plaque morphology, calcium distribution, and stent wall apposition with microscopic clarity.
Consequently, Sterile Cardiac Catheterization Hardware & Precision Instruments
Similarly, explore the sub-millimeter diagnostic catheters, hydrophilic sheaths, and arterial closure devices utilized during cardiac catheterization.
Notably, Hydrophilic-Coated Radial Sheath
In contrast, ultra-thin walled, low-friction polymer sheath designed for atraumatic radial cannulation. Ultimately, minimizes arterial spasm and post-procedure discomfort.
- Outer Diameter: Similarly, ~2.0–2.4 mm (5F–6F)
- Coating: Ultimately, cross-linked hydrophilic slippery coating
- Features: Overall, integrated silicone backbleed hemostasis valve
- Clinical Role: Meanwhile, stable entry port for all diagnostic catheters
Similarly, Precision Arterial Access Needle
Overall, ultra-fine gauge needle paired with 0.021” nitinol wire for precision single-wall puncture under palpation or ultrasound guidance.
- Needle Caliber: Subsequently, 21-Gauge bevel-ground surgical steel
- Safety: With this in mind, front-wall puncture reduces posterior hematoma risk
- Entry Profile: Specifically, minimal vessel trauma, rapid hemostasis
- Clinical Role: Furthermore, initial micro-access into radial/femoral lumen
Ultimately, Judkins Left Coronary Catheter
Pre-shaped curvature tailored to naturally seek and engage the Left Main Coronary Artery (LMCA) ostium from the ascending aorta.
- Construction: Additionally, braided stainless-steel wire for 1:1 torque
- Tip Safety: Consequently, soft, atraumatic non-tapered radiopaque tip
- Primary Targets: Moreover, left Anterior Descending (LAD) & Circumflex (LCx)
- Cine Views: Therefore, RAO Caudal, LAO Cranial, Spider views
Overall, Judkins Right (JR 4.0) & Tiger / Jacky Catheters
Meanwhile, specialized curves for right coronary artery cannulation and universal single-catheter radial solutions that image both arteries without catheter exchange.
- Tiger / Jacky Tip: In particular, angled secondary bend for dual-coronary imaging
- Torque Response: Notably, high rotational responsiveness with minimal friction
- Patient Benefit: In addition, reduces procedure time and catheter exchange cycles
- Safety Limit: Accordingly, continuous pressure monitoring to verify un-damped flow
Meanwhile, Diagnostic Conduit Guidewire
Subsequently, flexible J-curved guidewire providing safe tracking through peripheral arterial branches up into the ascending aortic root.
- Core Wire: Similarly, spring-coil stainless steel with PTFE coating
- Tip Design: Ultimately, 1.5–3.0 mm atraumatic soft J-curve
- Safety Feature: Overall, deflects away from vessel wall bifurcations
- Clinical Role: Meanwhile, leads diagnostic catheters safely to the aorta
Subsequently, Micro-Coronary Steerable Guidewire
Indeed, ultra-thin nitinol wire with shaping ribbon used when physiological assessment (FFR/iFR) or therapeutic stenting is indicated.
- Diameter: Subsequently, 0.014 inches (~0.36 mm)
- Tip Visibility: With this in mind, gold or platinum radiopaque distal coils
- Sensor Technology: Specifically, micro-piezoelectric pressure sensor for FFR
- Clinical Role: Furthermore, crosses tight coronary blockages safely
Indeed, Pneumatic Compression Radial Band
Transparent dual-balloon compression cuff providing targeted pressure over the radial puncture while maintaining distal palmar blood flow.
- Mechanism: Additionally, selective pneumatic air bladder inflation (~12–15 mL)
- Visibility: Consequently, clear window allows continuous site inspection
- Protocol: Moreover, incremental deflation over 2 to 3 hours
- Safety Goal: Therefore, 100% prevention of radial artery occlusion (RAO)
Clearly, Femoral Collagen / Suture Closure Devices
With this in mind, active closure systems (Angio-Seal, Perclose) delivering bio-absorbable collagen or surgical sutures directly to the femoral arteriotomy.
- Deployment Time: In particular, immediate mechanical sealing (<2 minutes)
- Ambulation: Notably, reduces bed rest from 6 hours to 2 hours
- Bio-Absorption: Naturally resorbed by the body within 60–90 days
- Clinical Benefit: In addition, drastically decreases groin hematoma rates
Specifically, Initial Assessment 1: Clinical Workup & Informed Consent for Cardiac Catheterization
Indeed, Pre-Cath Workup • ~15 MinsTo clarify, the interventional cardiologist reviews patient symptoms, detailed medical history, previous ECG/echo investigations, baseline renal profiles, anticoagulant regimens, contrast allergies, and confirms informed procedural consent.
Subsequently, Sterile Preparation 2: Local Anesthesia & Site Draping for Cardiac Catheterization
Clearly, Local Infiltration • Pain-FreeIn fact, the patient is comfortably positioned on the fluoroscopy table under multi-parameter vital telemetry. Specifically, after sterile surgical prep, a rapid-acting local anesthetic numbs the radial wrist or femoral access site; mild conscious sedation is administered if indicated.
Next, Arterial Access 3: Sheath Insertion & Catheter Navigation in Cardiac Catheterization
Subsequently, Fluoroscopic TrackingFurthermore, a slender micro-puncture sheath (5F/6F) is gently placed into the artery. Additionally, under live low-dose X-ray fluoroscopic guidance, a specialized diagnostic catheter is smoothly advanced through arterial conduits to the coronary ostia without vessel discomfort.
Furthermore, Diagnostic Imaging 4: Coronary Cineangiography & Hemodynamic Pressure Recording
Generally, 4K Digital Cine • WaveformsConsequently, radiopaque contrast agent is selectively injected into the coronary tree from multiple synchronized C-arm angles. Real-time digital cineangiograms record arterial blockages while high-fidelity transducers capture intracardiac chamber pressures and oxygen saturation gradients.
Then, Therapeutic Intervention 5: Real-Time Review & Immediate Stenting (PCI)
In fact, Immediate Stenting OptionMoreover, the cardiologist immediately reviews lesion severity and blood flow dynamics. Therefore, if a critical blockage is identified and indicated, the physician can seamlessly proceed with balloon angioplasty and precision drug-eluting stent (DES) implantation during the same procedure.
Finally, Hemostatic Closure 6: Sheath Removal & Band Placement After Catheterization
Ultimately, Targeted HemostasisIn particular, the diagnostic catheter and sheath are carefully withdrawn. For example, hemostasis is achieved using an adjustable pneumatic compression band (radial TR-Band) or vascular closure device. As a result, the patient is transferred to step-down recovery for monitored vital observation.
Specifically, Cardiac Catheterization Preparation: 3-Phase Clinical Protocol
In addition, proper clinical preparation significantly reduces procedural complications, ensures contrast safety, and allows the catheterization team to individualize vascular access and sedation strategies.
Specifically, Clinical Screening & Medication Review
Notably, baseline lab assessment and individual medication review conducted by your cardiology care team.
- Accordingly, Renal & Allergy Screening: Serum creatinine, eGFR evaluation, and detailed history of previous iodine or contrast material allergies.
- Similarly, Medication Management: Cardiologist-guided titration of blood thinners (Warfarin, NOACs) or diabetic medications (Metformin).
- Ultimately, Transportation Escort: Pre-arrange an adult companion for safe post-discharge transportation home following sedation.
Furthermore, Fasting, Hydration & Site Preparation
Accordingly, strict adherence to fasting guidelines to ensure airway safety during conscious sedation.
- Strict Fasting (NPO): No solid food for 6 to 8 hours prior; clear sips of water only if specifically approved for morning cardiac pills.
- Overall, Skin Hygiene & Care: Antimicrobial shower morning of the procedure; do not shave groin or wrist (clinical clippers used on-site).
- Meanwhile, Comfortable Clothing: Wear loose clothing and leave all jewelry, rings, and metal accessories at home.
Additionally, Pre-Cath Hospital Intake & Telemetry
Similarly, final vital telemetry checks and sterile preparation before entering the digital Cath Lab suite.
- Subsequently, IV Cannulation & Baseline ECG: Peripheral intravenous line placed for fluid hydration and emergency medication delivery.
- With this in mind, Informed Consent Briefing: Final discussion with the interventional cardiologist reviewing the procedure and access plan.
- Specifically, Cath Lab Transfer: Transfer to sterile fluoroscopy suite, local anesthesia infiltration, and sterile drape positioning.
Moreover, Patient Day-Of Cardiac Catheterization Readiness Checklist
In contrast, verify essential intake items before departing for the Henotic Cath Lab suite.
Therefore, Pre-Cardiac Catheterization Medication Management: Hold vs. Continue Protocol
Ultimately, certain daily medications interact with fluoroscopic contrast media or vascular access puncture sites. Overall, always confirm individual titration with your Henotic cardiologist:
Consequently, Anticoagulants & Antiplatelet Agents
Specifically, Warfarin, Eliquis (Apixaban), Xarelto (Rivaroxaban), Pradaxa (Dabigatran), ClopidogrelMoreover, Diabetic Medications & Contrast Nephropathy Protection
Specifically, Metformin, SGLT2 Inhibitors, Sulfonylureas, InsulinSpecifically, Blood Pressure & Hemodynamic Regulators
Furthermore, Beta-Blockers, ACE Inhibitors, ARBs, Calcium Channel Blockers, StatinsSpecifically, Herbal Supplements, Vitamins & NSAIDs
Furthermore, Omega-3 Fish Oil, Vitamin E, Ginkgo Biloba, Ginseng, IbuprofenIn particular, Important Medication Warning for Cardiac Catheterization Patients
Meanwhile, never stop prescribed medication or change a dose without instructions from the treating clinician. Fasting requirements and medication adjustments vary by procedure and individual circumstances.
Notably, Is Cardiac Catheterization Painful?
Subsequently, Cardiac catheterization is commonly performed using local anaesthesia at the insertion site. Indeed, patients may experience a brief sting when the anaesthetic is administered, along with pressure or mild discomfort during catheter insertion.
Furthermore, 1. Local Numbing Infiltration
With this in mind, a fine micro-needle administers local anesthetic (Lignocaine) at the puncture site (wrist or groin). To clarify, patients feel a quick initial sting, followed by total local numbness within seconds.
Notably, 2. Arterial Advancement
In fact, arteries lack interior pain nerve receptors. Specifically, once through the skin, catheter advancement through the vascular tree to the heart coronary ostia is painless; patients only perceive mild pressure.
Similarly, 3. Radiopaque Dye Flushing
Furthermore, as the radiopaque contrast agent is injected under fluoroscopy, a distinctive warm flush or mild metallic taste travels through the body. Additionally, this is completely normal and dissipates in 20–30 seconds.
Ultimately, 4. Anxiolytic Conscious Sedation
If requested or indicated, mild intravenous sedation helps eliminate procedure anxiety while keeping the patient conscious, breathing independently, and able to respond to physician guidance.
In addition, some patients experience a warm sensation when contrast material is injected. Notably, if sedation is used, it may help reduce anxiety and discomfort.
Accordingly, the experience differs from person to person. Similarly, patients should tell the clinical team immediately if they experience significant pain, breathing difficulty, or unusual discomfort during the procedure.
Similarly, Procedural Safety: Cardiac Catheterization Risks & Precautions
However, Cardiac catheterization is routinely performed when clinically indicated, but it is an invasive procedure and is not entirely risk-free.

Furthermore, Minor Puncture Hematoma & Bruising
Ultimately, localized skin bruising, mild subcutaneous hematoma, or transient access tenderness at the wrist or groin puncture site.
Additionally, Contrast Reaction & Vasovagal Response
Overall, mild cutaneous urticaria (itching or hives) in response to radiopaque contrast dye, transient nausea, or minor vasovagal dizziness.
Consequently, Renal Elevation & Vessel Complications
Meanwhile, contrast-induced acute kidney elevation, small pseudoaneurysm formation, or transient benign rhythm disturbances during catheter transit.
Moreover, Major Cardiovascular Events
Subsequently, Coronary arterial dissection, acute myocardial infarction, embolic stroke, or emergency cardiac surgery during diagnostic catheterization.
The overall risk depends on the patient’s condition, the urgency of the procedure, kidney function, the type of catheterization, and whether an intervention is performed.
Indeed, the treating cardiologist should explain the expected benefits, material risks, and available alternatives before the procedure, except where emergency circumstances require immediate action.
Similarly, ALARA Radiation Protection & Kidney Shielding in Cardiac Catheterization
With this in mind, AERB-regulated institutional benchmarks maintaining minimum radiation exposure and contrast safety.
Pulsed Low-Dose Fluoroscopy
State-of-the-art C-arm system uses digital pulsed exposure (7.5–15 pulses/sec) rather than continuous beam, slashing cumulative radiation dose while preserving 4K coronary resolution.
Low-Osmolar Contrast Agents
To clarify, exclusively non-ionic, low-osmolar contrast media calibrated to patient body mass index and baseline eGFR levels to protect delicate renal tubules and eliminate allergic reactions.
Ceiling Scatter & Pelvic Shields
In fact, lead-acrylic suspended radiation barriers, thyroid shields, and bismuth organ covers minimize secondary scatter radiation to both patient and catheterization personnel.
Dose Area Product (DAP) Telemetry
Specifically, multi-channel ionization chambers measure real-time Gy·cm² dose exposure with automated alarms, fully documented in your permanent Henotic digital radiology record.
Therefore, Kidney Nephron Hydration & Contrast Clearance Roadmap
Furthermore, evidence-based hydration schedule safeguarding renal tubules before, during, and after dye exposure.
Additionally, pre-hydrates intravascular volume to dilute initial contrast load upon cardiac injection.
Consequently, calibrated infusion (1.0 mL/kg/hr) maintains continuous glomerular filtration during fluoroscopy.
Moreover, accelerates natural urinary dye elimination; >99% of contrast is safely excreted within 24 hours.
Ultimately, Cardiac Catheterization Recovery: Access-Specific Pathways
Overall, recovery depends on the vascular access site, the procedure performed, the patient’s individual hemodynamic stability, and whether coronary stenting was performed.
Meanwhile, after the procedure, the clinical team monitors vital signs, access site hemostasis, and peripheral pulses in the affected limb.
Additionally, Radial Artery Recovery Protocol
Primary clinical access route (>85% of cases) offering earlier ambulation and reduced bleeding risk.
| Specifically, Bed Rest Time | Accordingly, 2 to 3 hours (Upright sitting permitted immediately) |
| Similarly, hemostasis Device | Ultimately, pneumatic TR-Band compression cuff (deflated incrementally) |
| Overall, discharge Status | Meanwhile, same-day discharge (4 to 6 hours post-procedure for diagnostic) |
| Furthermore, Physical Limit | Subsequently, avoid lifting > 5 kg with the affected wrist for 48 hours |
Consequently, Femoral Artery Recovery Protocol
Subsequently, utilized when radial access is anatomically tortuous, small-caliber, or for large-bore devices.
| Additionally, Bed Rest Time | With this in mind, 4 to 6 hours (Strict flat supine position with leg straight) |
| Specifically, hemostasis Device | Furthermore, manual compression, mechanical clamp, or collagen vascular closure plug |
| Additionally, discharge Status | Consequently, late same-day or overnight observation depending on sheath size |
| Strictly, Physical Limit | Moreover, avoid stairs, squatting, and strenuous exertion for 48 to 72 hours |
Overall, Post-Catheterization Milestone Roadmap & Activity Clearance
Indeed, select a recovery phase below to review evidence-based clinical protocols, permitted activities, wound care rules, and return-to-work guidelines.
Moreover, Immediate Protocol 1: Direct Hemostasis, Monitoring & Hydration Protocol
With this in mind, primary focus is securing absolute arterial seal at the access site, continuous hemodynamic rhythm monitoring, and eliminating radiopaque contrast media through high oral fluid hydration.
- Wrist Elevation: Furthermore, keep wrist in a neutral, supported resting position on a bedside arm pillow.
- Contrast Dye Washout: Additionally, drink 1.5 to 2.0 Liters of water or oral fluids unless on strict heart-failure fluid limits.
- Radial Band Protocol: Consequently, gradual deflation of the TR-Band (2 mL air released every 15 minutes by nursing staff).
- Early Light Nutrition: Moreover, clear fluids or light meal once local sedation and nausea subside completely.
- No Puncture Site Flexion: Therefore, strictly avoid bending the wrist or pushing off bed with the punctured hand.
- Strictly Zero Unassisted Ambulation: In particular, do not get out of bed without primary nurse supervision and stable blood pressure check.
- Zero Heavy Gripping: Notably, do not lift luggage, mobile chargers, or heavy electronics using the punctured arm.
- Femoral Access Rule: In addition, if groin access was utilized, maintain strict supine position with straight leg for 4–6 hours.
- Radial Pulse Check: Accordingly, verification of distal radial/ulnar pulse and capillary refill (<2 seconds) every 15 mins.
- Continuous ECG Telemetry: Similarly, sT-segment monitoring to confirm absence of procedural ischemia or arrhythmias.
- Blood Pressure & O2 Saturation: Ultimately, automated non-invasive BP cycle every 30 minutes.
- Discharge Readiness: Overall, ambulation trial without hematoma, dizziness, or vasovagal drop.
Therefore, Healing Stage 2: Post-Discharge Rest, Wound Care & Dressing Management
To clarify, following discharge, focus shifts to protecting the puncture seal, managing mild local tenderness, monitoring for unexpected swelling, and gradually resuming light household activities.
- Dressing Inspection: Meanwhile, keep the transparent sterile puncture dressing clean, intact, and dry for 24 hours.
- Gentle Showering: Subsequently, quick lukewarm shower permitted after 24 hours; gently pat the site dry with a clean towel.
- Light Ambulation: With this in mind, leisurely indoor walking is encouraged to stimulate circulation and prevent deep vein stasis.
- Mild Pain Relief: Specifically, paracetamol (500–650 mg) as prescribed for localized wrist or groin tenderness.
- Water Submersion Restriction: Furthermore, strictly avoid bathtubs, swimming pools, hot tubs, or ocean bathing for 5 full days.
- Physical Straining Prevention: Additionally, avoid vigorous coughing, heavy bowel straining, or lifting objects heavier than 2 kg.
- Topical Care Protocol: Furthermore, do not scrub, apply ointments, powders, or herbal pastes over the puncture wound.
- Zero Motor Vehicle Driving: Additionally, do not operate a car, motorcycle, or machinery for at least 48 hours post-sedation.
- Expanding Hematoma: Consequently, any firm, rapidly growing lump under the puncture site exceeding a coin diameter.
- Active Oozing: Moreover, continuous blood seepage that does not cease after 10 minutes of direct firm manual pressure.
- Neurovascular Deficit: Therefore, pallor, coldness, tingling, or loss of sensory perception in fingers or toes.
- Fever > 100.4°F (38°C): In particular, clinical indicator of potential superficial infection or thrombophlebitis.
In Particular, Functional Clearance 3: Work Resumption, Driving Guidelines & Daily Independence
Patients resume sedentary occupational activities, driving (subject to clinical verification), and expanded domestic tasks while continuing arterial protection and dual antiplatelet therapy.
- Desk & Office Work: Notably, resumption of computer work, typing, meetings, and light managerial duties.
- Driving Clearance: In addition, resuming driving after 48 hours for diagnostic angiograms (7 days if coronary stent was deployed).
- Moderate Walking: Accordingly, brisk flat-surface walking for 15–30 minutes daily to maintain aerobic conditioning.
- Medication Adherence: Similarly, strict daily intake of prescribed antiplatelet agents (Aspirin + Clopidogrel/Ticagrelor).
- Lifting Limit < 5 kg: Ultimately, do not lift heavy grocery bags, carry luggage, or lift small children with the affected arm.
- Athletic Activity Clearance: Specifically, avoid tennis, golf, weightlifting, running, push-ups, or contact sports until clinically cleared.
- Prescription Adherence: Moreover, never skip or pause antiplatelet blood thinners without direct cardiologist consent.
- Long-Haul Travel Guidance: Finally, refrain from commercial flights exceeding 4 hours without clinical thrombosis prophylaxis review.
- Wound Assessment: Puncture site scab will naturally separate; pink healthy skin marks complete epithelial seal.
- Review Appointment: Overall, day 5–7 outpatient consultation with Specifically, Dr. Siddharth Sonkamble for catheterization review.
- Lipid & Renal Profile: Meanwhile, follow-up Serum Creatinine test if baseline kidney function was borderline.
- DAPT Prescription Refill: Subsequently, ensure uninterrupted 12-month supply of antiplatelet therapies if stented.
In Addition, Phase 4: Cardiac Rehabilitation, Exercise Escalation & Lifestyle Optimization
In fact, long-term cardiovascular risk reduction, progressive aerobic exercise reconditioning, structured dietary guidance, and routine cardiological surveillance.
- Cardiac Rehabilitation: With this in mind, enrollment in Phase II structured supervised exercise and nutrition conditioning.
- Full Physical Activity: Specifically, resumption of gym workouts, swimming, cycling, and vigorous recreational sports.
- Heavy Manual Labor: Furthermore, clearance for heavy lifting, overhead construction, and physical industrial trades.
- Targeted Lipid Control: Additionally, attainment of LDL Cholesterol target (<55 mg/dL for post-PCI coronary disease).
- No Premature Stent Stoppage: Consequently, premature discontinuation of DAPT causes catastrophic stent thrombosis.
- Zero Tobacco Exposure: Moreover, absolute avoidance of smoking and secondhand smoke to prevent restenosis.
- Avoid Unmonitored Supplements: Therefore, do not consume high-dose Vitamin E, Ginkgo, or unverified herbal extracts that compound bleeding.
- Zero Ignoring Angina Recurrence: In particular, immediately report any recurrence of exertional chest pressure or dyspnea.
- Blood Pressure Target: Notably, SBP < 130 mmHg and DBP < 80 mmHg consistently on home monitoring.
- Glycemic Optimization: In addition, hbA1c < 7.0% (or personalized target) for patients with concurrent Type 2 Diabetes.
- Repeat Stress Testing: Accordingly, optional non-invasive myocardial perfusion scan at 6–12 months as indicated.
- 24/7 Concierge Hotline: Similarly, ongoing priority clinical support via Henotic Diagnostics (+91 8879327184).
Meanwhile, General Aftercare Guidelines Following Cardiac Catheterization
-
Specifically, follow all instructions regarding movement, lifting, bathing, and wound care.
-
Furthermore, keep the access site clean and follow the recommended dressing instructions.
-
Additionally, take prescribed medicines exactly as directed.
-
Drink fluids according to the clinical team’s advice, particularly if fluid intake is restricted because of a heart or kidney condition.
-
Consequently, attend scheduled follow-up appointments.
-
Moreover, ask when it is safe to resume work, driving, exercise, and normal daily activities.
For example, note: Recovery instructions differ for wrist and groin access and may be more restrictive after coronary intervention.
Overall, Comparative Modalities: Cardiac Catheterization vs. Other Heart Tests
Accordingly, different cardiac tests answer different clinical questions. Similarly, the appropriate investigation depends on the suspected condition and the information needed.
Meanwhile, 12-Lead Electrocardiogram (ECG)
Indeed, records myocardial surface electrical conduction, acute ST-elevation, arrhythmias, and conduction blocks.
Subsequently, 2D Echocardiography & Color Doppler
With this in mind, real-time ultrasound evaluation of myocardial contractility, ejection fraction (LVEF %), heart valves, and chamber dimensions.
Indeed, Stress Testing (TMT / Stress Echo)
To clarify, assesses inducible myocardial ischemia, functional exercise capacity, and ST-segment depression under physical workload.
Clearly, Coronary CT Angiography (CCTA)
In fact, 3D multi-slice volumetric reconstruction of coronary lumen, Agatston calcium scoring, and soft plaque characterization.
Specifically, Cardiac Catheterization & Coronary Angiography
Specifically, direct selective cinefluoroscopy with sub-millimeter arterial resolution (0.1 mm), intracardiac pressure telemetry, and fractional flow reserve (FFR).
Furthermore, these tests are not interchangeable in every clinical situation. Additionally, Cardiac catheterization may be recommended when its findings are expected to provide information that non-invasive testing cannot adequately supply or when an invasive treatment may be needed.
Meanwhile, Who May Need Cardiac Catheterization? Clinical Candidacy Guide
Consequently, Cardiac catheterization is an invasive diagnostic and therapeutic procedure indicated when non-invasive tests require definitive anatomical verification or when direct intravascular pressure measurements are essential for treatment planning.
Generally, Emergency Indications for Urgent Cardiac Catheterization
Moreover, immediate primary catheterization indicated to re-establish coronary perfusion and limit myocardial damage.
- Moreover, Acute STEMI / High-Risk NSTEMI: Active myocardial infarction with coronary occlusion requiring primary angioplasty (PCI).
- Therefore, Refractory Unstable Angina: Ongoing acute ischemic chest pain unresponsive to maximal medical therapy.
- In particular, Cardiogenic Shock: Severe acute heart pump failure or post-resuscitation hemodynamic collapse.
In fact, Elective Indications for Diagnostic Cardiac Catheterization
Therefore, outpatient risk-stratified workup following abnormal preliminary non-invasive cardiac investigations.
- Notably, High-Risk Stress Testing: Marked ST depression or ischemic dysfunction during TMT or Stress Echocardiography.
- In addition, Equivocal CT Angiography: Severe calcification (Agatston >400) or intermediate stenosis requiring FFR flow verification.
- Accordingly, Severe Valvular Disease: Hemodynamic pressure gradients before aortic or mitral surgical/TAVI intervention.
- Similarly, Unexplained Pulmonary Hypertension: Right heart catheterization for pulmonary vascular resistance assessment.
As a result, Relative Delay Factors
In particular, conditions requiring clinical stabilization and medical optimization prior to elective catheterization.
- Ultimately, Acute Renal Impairment: Requires pre-procedure IV bicarbonate hydration to prevent contrast-induced nephropathy.
- Overall, Active Coagulopathy or Bleeding: Elevated INR or severe thrombocytopenia requiring anticoagulant withholding.
- Meanwhile, Active Systemic Sepsis / Fever: High bacteremia risk requiring anti-infective treatment prior to vascular access.
- Uncontrolled Hypertension: Systolic BP >180 mmHg requiring oral/IV antihypertensive titration first.
Furthermore, the decision for catheterization is made in close partnership with your treating cardiologist, balancing clinical necessity, expected diagnostic yield, and individualized procedural safety.
Subsequently, Our Cardiac Catheterization Accreditations & Quality Standards
Additionally, Henotic Diagnostics operates in strict alignment with national statutory healthcare authorities and premier clinical accreditation bodies. Consequently, our cardiac diagnostic suites, fluoroscopic catheterization infrastructure, pathology calibration standards, and interventional protocols undergo rigorous continuous auditing to guarantee uncompromising patient safety, diagnostic accuracy, and radiation protection.
Furthermore, Statutory Healthcare Accreditations for Cardiac Catheterization Facilities
Moreover, verified institutional accreditations governing our cardiac diagnostics, laboratories, and imaging facilities.

Additionally, Atomic Energy Regulatory Board (AERB)
Therefore, strict statutory compliance for cardiac fluoroscopy systems, C-arm scatter radiation shields, low-dose cine-angiography protocols, and bi-annual safety audits.

Consequently, NABH Healthcare Standards
In particular, adherence to national benchmarks in patient care governance, sterile surgical air filtration (HEPA filters), emergency resuscitation readiness, and informed clinical consent.

Moreover, NABL Testing & Calibration
For example, rigorous multi-point quality assurance for pre-procedure blood panels, cardiac biomarker assays (hs-cTnI, CK-MB, Lipid Profiling), and hemodynamic pressure sensor calibrations.

Therefore, ISO 9001:2015 Quality Systems
As a result, standardized quality management systems overseeing patient scheduling, contrast injection verification protocols, clinical documentation integrity, and post-procedure surveillance.
Specifically, Official Diagnostic Licenses & Accreditation Certificates
Furthermore, direct view of active clinical registrations and regulatory compliance certificates at Henotic Diagnostics.





In addition, Cardiac Catheterization Quality Indicators & Safety Metrics
Notably, our catheterization laboratory strictly audits procedural safety, diagnostic accuracy, and radiation hygiene against international ACC/AHA and national NABH benchmarks:
Transradial-First Access Rate
Accordingly, primary wrist route utilization minimizing access-site hematoma, enabling immediate post-cath sitting, and lowering vascular bleeding complications.
Meanwhile, Door-to-Balloon Time (Emergency STEMI)
Similarly, average time from patient hospital arrival to balloon catheter inflation in acute myocardial infarction, saving critical heart muscle tissue.
Subsequently, Contrast Nephropathy Prevention
In contrast, patients maintaining baseline renal function post-cath through iso-osmolar non-ionic contrast agents and protocolized pre/post saline hydration.
Indeed, Spatial Diagnostic Resolution
Ultimately, flat-panel digital cinefluoroscopy providing sub-millimeter lumen visualization to detect microvascular lesions, plaque ulceration, and dissection flap edges.
Consequently, AERB Real-Time Radiation Hygiene Governance
All fluoroscopic equipment operates with pulsed fluoroscopy (7.5–15 pulses/sec) rather than continuous beam exposure, reducing cumulative radiation dose by up to 60%. With this in mind, dose Area Product (DAP) meters continuously display patient milligray absorption on the primary surgical monitor.
Moreover, NABH Infection Control & Single-Use Consumable Assurance
To clarify, zero reuse policy: all diagnostic catheters, guide wires, radial sheaths, and balloon inflation devices are 100% single-use, sterile-packaged, and barcode-scanned to each patient’s electronic health record. In fact, the Cath Lab suite features HEPA-filtered laminar airflow maintaining Positive Pressure ISO Class 7 air cleanliness.
Therefore, Cardiovascular Clinical Audits & Multidisciplinary Peer Review
Specifically, every diagnostic coronary angiogram with borderline lesions (50%–70%) or multi-vessel involvement is evaluated by the multidisciplinary Heart Team (Interventional Cardiologist, Cardiothoracic Surgeon, and Non-Invasive Cardiac Imaging Specialist) to select the safest, most durable intervention.
Similarly, Continuous Clinical Quality Audits
Furthermore, all catheterization consumables, pre-lubricated diagnostic catheters, vascular sheaths, radiopaque contrast lots, and automated external defibrillators undergo batch-certified tracking in accordance with ISO 13485 and NABH infection control mandates.
Indeed, Cardiac Catheterization Patient Testimonials & Verified Experiences
For example, discover how our advanced fluoroscopic accuracy, gentle wrist radial access, and compassionate nursing care empower patients across Navi Mumbai and Mumbai through safe, stress-free cardiac diagnostics.
Overall, Catheterization Clinical Registry Outcomes & Quality Benchmarks
Meanwhile, Verified Patient Recovery Experiences and Clinical Stories
&As a result, ldquo;I was extremely anxious when my cardiologist advised a coronary angiogram for persistent chest discomfort. In addition, the cardiac team at Henotic Diagnostics made me feel completely at ease. Notably, they used wrist radial access, and the local anaesthesia was barely a pinch. Dr. Accordingly, siddharth Sonkamble walked me through my coronary scan results immediately after. Similarly, i was discharged the same afternoon with absolute peace of mind.”

&In contrast, ldquo;After an abnormal treadmill stress test, I required a definitive cardiac catheterization. Ultimately, the Cath Lab environment at Henotic was spotless, calm, and equipped with impressive fluoroscopy technology. Overall, the nursing staff kept monitoring my vitals continuously, and the whole procedure was finished in under 40 minutes. Truly a gold standard experience in cardiac care.”

Notably, Senior Patient Care & Right Heart Catheterization Feedback
&Meanwhile, ldquo;I had unexplained breathlessness for months and needed a right heart catheterization to measure pulmonary pressures. Subsequently, the doctors explained every preparatory step with immense patience. Indeed, during the procedure, I felt no pain at all, just slight pressure. With this in mind, their gentle clinical approach made what felt like an intimidating test completely manageable.”

Subsequently, Long-Term Recovery & Cardiac Catheterization Patient Outcomes
Additionally, Multivessel Angioplasty & Emergency Clinical Stories
&To clarify, ldquo;When my ECG showed signs of ischemia, Henotic Diagnostics arranged my cardiac catheterization without unnecessary delays. In fact, the clarity of their cineangiography scans pinpointed the exact location of narrowing. Dr. Sonkamble explained our next therapeutic options in plain language without rushing. Their professional integrity is truly commendable.”

&Specifically, ldquo;My biggest fear about cardiac catheterization was the recovery period and potential bleeding. Furthermore, the medical team applied a specialized wrist compression band after catheter removal, and I had zero bruising. Additionally, the post-procedure observation ward was comfortable, quiet, and attentive. Consequently, i’m grateful for their compassionate and precise care.”

&Moreover, ldquo;I chose Henotic Diagnostics for an elective coronary catheterization based on their AERB and NABH accreditations. Therefore, from the initial fasting instructions to the discharge summary, everything operated like clockwork. In particular, knowing that the Cath Lab followed rigorous international radiation and sterile protocols gave my family tremendous confidence.”

Clearly, Frequently Asked Questions About Cardiac Catheterization
For example, review comprehensive clinical answers to 13 essential patient inquiries regarding the procedure, pain management, risks, and recovery expectations.
As a result, its main purpose is to investigate cardiovascular conditions by examining coronary arteries, measuring pressures within the heart and pulmonary circulation, or obtaining other selected diagnostic information. In some cases, it also provides a route for treatment.
No. In addition, Coronary angiography is a specific imaging procedure that can be performed as part of cardiac catheterization. Notably, Cardiac catheterization is a broader term that includes other diagnostic and therapeutic procedures.
Accordingly, the duration varies with the type of procedure, the complexity of the findings, and whether treatment is performed. Similarly, the clinical team can provide a more appropriate estimate based on the planned procedure.
Consequently, Procedural Sensation & Anesthesia Inquiries
It is generally a minimally invasive procedure rather than open-heart surgery. However, it remains an invasive cardiovascular procedure with potential complications and requires appropriate clinical facilities and monitoring.
However, general anaesthesia is not routinely required for many standard diagnostic catheterization procedures. Ultimately, local anaesthesia is commonly used, with sedation when appropriate. Overall, the anaesthesia plan depends on the procedure and the patient’s clinical needs.
Meanwhile, Coronary angiography can identify narrowing or blockage in the coronary arteries. Subsequently, the significance of each finding depends on its location, severity, effects on blood flow, and the patient’s symptoms and other clinical findings.
Indeed, Cardiac Catheterization Safety, Fasting & Recovery Inquiries
No. Indeed, diagnostic catheterization does not automatically involve stent placement. With this in mind, a stent may be considered when coronary intervention is appropriate, based on the clinical findings, treatment strategy, and informed consent.
To clarify, follow the specific fasting and fluid instructions provided by the treating team. In fact, requirements can differ depending on the planned procedure, sedation, and individual health conditions.
Recovery may take several hours for initial monitoring, while full recovery and activity restrictions depend on the access site, the procedure, and whether treatment was performed. Follow the discharge instructions rather than a fixed timetable.
Specifically, kidney disease can increase the risk of contrast-associated kidney complications. Furthermore, the clinical team assesses kidney function and considers appropriate precautions, contrast use, and alternative approaches when indicated.
Moreover, Long-Term Recovery, Driving & Work Clearance Guidance
Additionally, it may be urgently indicated in selected patients with acute coronary syndromes, including certain heart attacks, or other serious cardiovascular conditions. Consequently, emergency decisions depend on clinical assessment and the expected benefit of immediate intervention.
Moreover, right heart catheterization primarily measures pressures and blood flow-related parameters on the right side of the heart and in the pulmonary circulation. Therefore, left heart catheterization can provide information about pressures on the left side and may be performed alongside coronary angiography, depending on the indication.
In particular, a qualified cardiologist or appropriate treating specialist makes the recommendation based on the patient’s clinical condition, test results, potential benefits, procedural risks, and available alternatives.
Generally, Why Choose an Evidence-Based Approach to Cardiac Catheterization?
Specifically, cardiovascular diagnosis requires a careful balance between clinical accuracy, patient safety, and appropriate use of investigations.
Notably, Henotic Diagnostics emphasizes clear, understandable information to help patients and families discuss cardiac investigations with qualified healthcare professionals.
Accordingly, an informed approach to cardiac care includes:
-
Similarly, understanding why a particular test has been recommended.
-
In contrast, reviewing relevant medical history and previous diagnostic findings.
-
Ultimately, discussing the benefits, risks, and alternatives to invasive procedures.
-
Overall, following individualized preparation and recovery instructions.
-
Meanwhile, ensuring that diagnostic findings are interpreted in the context of the patient’s clinical condition.
Clearly, ACC / AHA Clinical Guideline Hierarchy for Cardiac Catheterization
Subsequently, every diagnostic recommendation and interventional threshold is classified according to international gold-standard clinical consensus tiers:
Meanwhile, Strong Clinical Mandate (“Is Recommended”)
Indeed, definitive evidence that cardiac catheterization improves survival and clinical outcomes. With this in mind, applied in acute STEMI (<90m primary PCI), non-ST elevation ACS with high-risk features, and refractory angina.
Subsequently, Moderate Clinical Recommendation (“Is Reasonable”)
To clarify, substantial evidence supports procedure value. In fact, applied in intermediate-risk coronary blockages where invasive Fractional Flow Reserve (FFR ≤ 0.80) or IVUS plaque imaging guides stenting.
Indeed, Clinical Restriction (“Not Recommended”)
Specifically, invasive catheterization is not recommended in completely asymptomatic patients with low pre-test clinical probability or normal stress testing, protecting patients from unnecessary invasive exposure.
Generally, Multidisciplinary Cardiac Catheterization Procedural Team
Furthermore, every cardiac catheterization at Henotic Diagnostics is conducted by a coordinated four-tier clinical unit.
Clearly, Primary Interventional Cardiologist
Overall, Lead Operator • MD, DMAdditionally, performs arterial cannulation, guides micro-catheters under fluoroscopy, records hemodynamics, and deploys drug-eluting stents.
Specifically, Cardiac Anesthesiologist
Meanwhile, Sedation & Airway LeadConsequently, administers calibrated conscious sedation, monitors real-time arterial oxygenation, and maintains continuous hemodynamic stability.
Furthermore, Cardiovascular Technologist
Subsequently, AERB Radiation & Cine SpecialistMoreover, controls digital C-arm angulation, calibrates multi-channel pressure transducers, and monitors ALARA radiation dose exposure meters.
Additionally, Critical Care Cath Nurse
Indeed, ACLS/BLS Certified Hemostasis NurseTherefore, maintains sterile procedural field, manages IV lines and emergency medications, and oversees post-procedure TR-Band compression recovery.
The choice of investigation should always be guided by clinical need rather than the assumption that a more invasive test is necessarily better.
As a result, Discuss Your Cardiac Catheterization Pathway with Our Cardiology Desk
Whether you require an initial catheterization evaluation, a second opinion on an existing coronary angiogram CD, or post-procedure recovery support, select your pathway below for direct medical team triage:
Ultimately, Elective & Priority Diagnostic Coronary Angiogram
Accordingly, designed for patients with chest discomfort, shortness of breath, unexplained fatigue, or positive stress test (TMT) / 2D Echo results needing definitive catheterization.
- Subsequently, previous ECG & 2D-Echocardiography reports
- With this in mind, recent serum creatinine & electrolyte levels (<30 days)
- Full list of active medications (especially anticoagulants or diabetes drugs)
Overall, Coronary Angiogram CD Review & Revascularization Triage
Similarly, comprehensive review with Dr. In contrast, siddharth Sonkamble (DM Cardiology) for complex anatomical decisions: multi-vessel disease, bifurcation stenting vs CABG, and SYNTAX score evaluation.
- Specifically, DICOM cineangiogram CD or cloud imaging link
- Furthermore, hospital formal angiogram report & previous discharge summary
- Additionally, diabetic status, renal profile, and current symptom log
Meanwhile, Post-Catheterization Home Care & Medication Follow-Up
Ultimately, support for patients recovering from radial or femoral catheterization: wound assessment, hematoma evaluation, dual antiplatelet therapy questions, and return-to-work clearance.
- Consequently, henotic discharge summary & prescription list
- Moreover, photo of access site (wrist/groin) if evaluating swelling or bruising
- Therefore, current blood pressure & heart rate telemetry readings
Accordingly, Medical Authority and Trust References
Overall, the clinical guidance, procedure indications, safety data, and preparation protocols presented on this page are strictly synthesized from internationally accredited interventional cardiology registries, national institutes of health, and consensus clinical practice guidelines.
Meanwhile, official clinical practice summary on cardiac catheterization indications, hemodynamic pressure recordings, and procedural safety.
Subsequently, diagnostic and interventional catheterization guidelines, coronary angiography protocols, and valvular heart disease evaluation.
Indeed, comprehensive patient education review on coronary angiography, left & right heart catheterization, and post-procedure wound care.
With this in mind, evidence-based clinical overview of transradial and transfemoral access approaches, contrast clearance precautions, and recovery timelines.
To clarify, patient decision guides, pre-catheterization checklists, and interventional cardiology appropriateness criteria.
Notably, clinical diagnostic specifications for heart catheterization, coronary stenting, fractional flow reserve (FFR), and recovery monitoring.
Ultimately, Consult With Our Cardiac Catheterization Care Team
Whether you have immediate clinical inquiries regarding cardiac catheterization, coronary angiography preparation, or need a second opinion review with Dr. Overall, siddharth Sonkamble, our diagnostic navigation team is here to assist.
Specifically, Henotic Diagnostics – Corporate Headquarters & Flagship Cardiac Center
Meanwhile, centrally located in Kharghar, Navi Mumbai to coordinate rapid pre-catheterization diagnostic workups, emergency cardiac enzyme profiling, and seamless Cath Lab admissions across Navi Mumbai, Panvel, and the Mumbai Metropolitan Region.
Overall, Regional Transit Connectivity & Emergency Cath Lab Admission Desk
Specifically, Multimodal Transit & Rapid Accessibility Routes
Furthermore, Flagship Center Facility Address & Operating Hours
Subsequently, continuous 24/7 processing for emergency Troponin-I, hs-cTn, Serum Creatinine / eGFR (contrast safety clearance), and PT/INR coagulation profiling.
Indeed, full pre-procedure workup including 12-Lead ECG, 2D Echocardiography with Color Doppler, Complete Hemogram, Renal Contrast Risk Profiling, and interventional cardiologist consultation coordination.
With this in mind, 24/7 doorstep phlebotomy across Kharghar, Belapur, Seawoods, Nerul, Vashi, and Panvel for mobility-restricted cardiac patients requiring urgent pre-procedure tests.
Additionally, Live GPS Facility Location & Navigation Map
Consequently, Cashless Mediclaim Empanelment & TPA Desk
Meanwhile, Cashless Insurance & TPA Desk for Cardiac Catheterization
To clarify, hassle-free insurance coordination, day-care claim clearance, and transparent package pricing.
Specifically, Pre-Authorization Clearance
In fact, on-site TPA coordinators submit clinical query responses and diagnostic dossiers directly to your insurer for same-day cashless approval.
Furthermore, Empaneled Insurance Networks
Specifically, accepting Star Health, HDFC ERGO, Care Health, ICICI Lombard, Niva Bupa, Medi Assist, Paramount, Vidal Health, and MDIndia.
Additionally, Standardized Package Inclusions
Furthermore, comprehensive coverage encompassing sterile radial kits, non-ionic contrast, fluoroscopy cine recording, day-care bed, and physician fees.
Consequently, Transparent Clinical Billing
Additionally, clear, pre-counseled estimate provided by your interventional team before entering the lab, with no surprise ancillary charges.